Dr. Vipulroy Rathod

Author name: Dr. Rathod Medical Foundation

What Is EUS Guided Celiac Block for Pain?

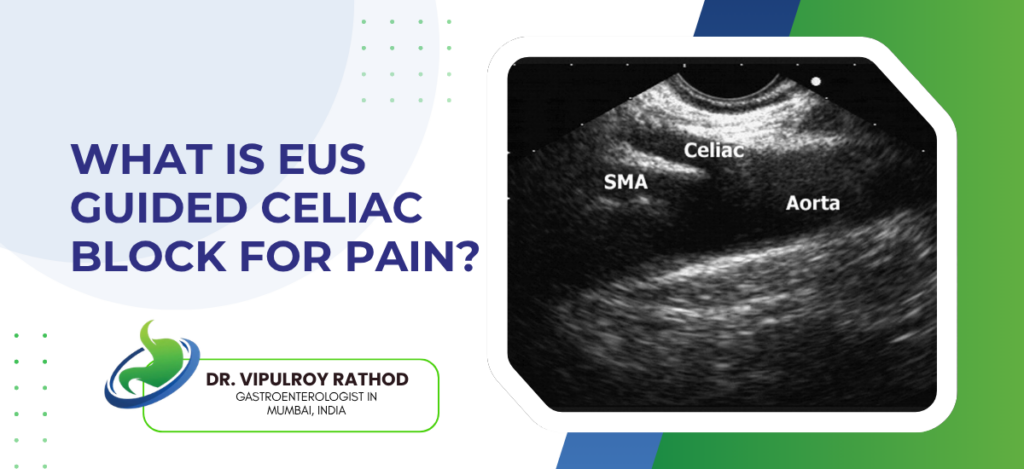
EUS-guided celiac plexus block is an endoscopic procedure that delivers a steroid and local anaesthetic injection, or sometimes a neurolytic agent, directly into the celiac plexus, the bundle of nerves carrying pain signals from the upper abdominal organs. It is used to control severe abdominal pain in patients with chronic pancreatitis and unresectable pancreatic cancer. The procedure replaces the need for escalating opioid doses in many patients, particularly those whose pain has stopped responding to standard medication. Done through endoscopic ultrasound rather than fluoroscopy or CT, the access is more direct and the targeting more precise than older percutaneous techniques. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Pancreatic pain is a different category from other abdominal pain. It comes from deep visceral nerves, doesn’t respond well to standard painkillers, and gets worse as the disease progresses. Celiac block targets the wiring directly. It doesn’t fix the cause, but it interrupts the signal, and for the right patient that’s life-changing.” Who benefits from EUS-guided celiac block? The two main indications are chronic pancreatitis and unresectable pancreatic cancer, but the type of injection used differs between them. Chronic pancreatitis with severe pain. Patients whose pain has stopped responding to enzyme replacement, analgesia, and lifestyle changes. The injection here is usually a steroid plus local anaesthetic combination, called a celiac block rather than neurolysis, and the effect lasts weeks to months. Some patients need repeat injections every few months. Unresectable pancreatic cancer pain is where neurolysis becomes appropriate. Absolute alcohol is injected to permanently damage the nerves, and pain control often lasts the rest of the patient’s life. The trade-off is that neurolysis is permanent and can’t be reversed if complications develop. Failure of medical pain management. Patients on rising opioid doses who are getting side effects without proper pain control. Celiac block lets opioid doses come down, often substantially, while pain stays better managed than before. Selected cases of locally advanced disease awaiting chemotherapy response, where pain control is needed urgently while definitive treatment plays out over months. The decision between block and neurolysis depends on the underlying disease and prognosis. Pancreatic cancer treatment planning in advanced disease almost always includes a conversation about pain management options, and celiac block fits early into that conversation rather than being a last resort after everything else has failed. How the procedure works and what to expect? EUS-guided celiac block is done under sedation, usually as a day-care procedure, taking around twenty to thirty minutes from start to finish. A linear-array echoendoscope is passed through the mouth into the stomach, positioned to image the celiac axis and the bundle of nerves surrounding it. Under real-time ultrasound guidance, a fine needle is advanced through the stomach wall to the area just around the celiac plexus. The injection is given, usually divided between two sites on either side of the celiac axis for better coverage. Then the needle is withdrawn. If you’re the patient, the experience is straightforward. You arrive in the morning, sedation goes in, you wake up in recovery an hour later, you go home by afternoon. Pain relief usually starts within twenty-four to forty-eight hours. Block (steroid plus anaesthetic) effects. Pain relief in around sixty to seventy percent of chronic pancreatitis patients, with effects lasting weeks to several months. Repeat injections work but with diminishing returns over multiple cycles. Neurolysis (alcohol injection) effects. Substantial pain relief in seventy to eighty percent of pancreatic cancer patients, with effects often lasting the duration of the illness. Some patients have no effect, and the lack of response is itself information about the source of the pain. Complications are uncommon but possible. Transient diarrhoea, hypotension after the procedure (from sympathetic blockade), occasional retroperitoneal bleed. Permanent paraplegia from spinal cord injury has been reported but is rare in EUS-guided cases compared to older posterior approaches. Repeat blocks are technically straightforward in chronic pancreatitis patients. Neurolysis, once done, is permanent and isn’t repeated. So the choice of agent depends on whether you’re treating a long-term condition or a terminal one. Read more on pancreatic cancer detection for how pain management decisions fit into the broader pathway of unresectable pancreatic disease. Why choose Dr. Vipulroy Rathod for EUS-guided celiac block? Dr. Vipulroy Rathod has been performing EUS-guided celiac block and neurolysis at Fortis Hospital Mulund for over three decades, covering both chronic pancreatitis cases and unresectable pancreatic cancer pain management. Many patients arrive on high doses of opioid medication, struggling with side effects and inadequate pain control, having never been offered celiac block as an option earlier in their disease course. The procedure isn’t a last resort. It works best when offered before pain becomes intractable, before opioid tolerance is fully established, before the patient’s quality of life has eroded too far. Timing matters as much as technique. Book your consultation today with one of India’s most experienced specialists for EUS-guided pain management and pancreatic disease care. Book Appointment Call now Frequently Asked Questions Is EUS-guided celiac block painful? The procedure itself isn’t, because it’s done under sedation. Some patients have transient abdominal discomfort for a day or two afterwards, which settles on its own. Severe pain after the procedure is uncommon and would need assessment. How long does the pain relief last? For chronic pancreatitis blocks, several weeks to several months, often with diminishing duration on repeat injections. For pancreatic cancer neurolysis, often the rest of the patient’s illness, though some patients need a second procedure if relief fades. Can the procedure be repeated? Steroid-based blocks for chronic pancreatitis can be repeated several times. Neurolysis with alcohol is generally a one-time procedure, though there are rare cases where it’s repeated when partial response occurred initially. What are the side effects? Diarrhoea and a drop in blood pressure are the most common, both usually mild and self-limiting. More serious complications like retroperitoneal bleeding or, very rarely, spinal cord injury, are uncommon in experienced hands using EUS guidance. Reference links- EUS-Guided Therapeutic Procedures Guidelines, American Society for Gastrointestinal Endoscopy —

What Is EUS Guided Celiac Block for Pain? Read More »

When Is a Pancreatic Stent Needed?

A pancreatic stent is needed when the pancreatic duct is blocked, narrowed, or leaking, and that obstruction is causing pain, recurrent pancreatitis, or interfering with drainage. The decision isn’t automatic. Some duct narrowings can be watched, others need urgent intervention, and the difference depends on symptoms, imaging, and whether the cause is something correctable on its own. Most stents go in during ERCP, sometimes with EUS guidance for difficult anatomy. The harder question for most patients isn’t whether stenting works, it’s whether they actually need one right now. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Stenting is overused in some centres and underused in others. A patient with mild chronic pancreatitis and minor duct changes doesn’t always need a stent. A patient with a tight stricture and recurrent pain definitely does. Getting that judgment right is what separates good pancreatic ERCP practice from procedural overuse.” Which are the Conditions that typically need stenting? The indications fall into a handful of clear categories, and most cases that get stented fall into one of these patterns. Dominant strictures in chronic pancreatitis. A localised narrowing of the main duct, often with upstream dilatation visible on MRCP, in a patient with ongoing pain. Stenting the stricture relieves pressure and pain in around sixty to seventy percent of cases. Pancreatic duct stones, particularly when they’re impacted and causing recurrent pancreatitis. Removal comes first, sometimes with shockwave lithotripsy if the stones are large or hard, then the stent goes in to keep the duct open while the inflammation calms down. Pancreatic duct leak or disruption. Trauma, surgery, or severe pancreatitis can tear the duct. Pancreatic juice then leaks into surrounding tissue, sometimes forming pseudocysts or causing ascites. A transpapillary stent across the leak point usually allows it to heal. Some pancreatic cancers compressing the duct. Not all of them, only the small subset where ductal pressure is causing pain or recurrent pancreatitis and surgery isn’t an option, often in patients on chemotherapy who need symptom control. Choosing which patients benefit isn’t always obvious from imaging alone. Pancreatic stone extraction work and stenting decisions usually happen together in the same procedure, with EUS sometimes added beforehand to assess the duct anatomy, exclude masses, and plan the approach properly. When stenting is the wrong answer? Not every blocked duct should be stented, and the reverse question matters as much as knowing when to do it. Asymptomatic minor duct changes. Mild narrowing on MRCP without pain, without recurrent pancreatitis, without functional impairment. Stenting these patients exposes them to procedure risk without clear benefit. Acute pancreatitis episodes themselves aren’t an indication for stenting in most cases. The duct usually clears on its own once inflammation settles. Premature stenting can make things worse rather than better. Diffuse strictures throughout the entire pancreatic duct. When the whole duct is narrowed rather than one focal segment, stenting one area doesn’t help much, and these patients often need surgical drainage rather than endoscopic stenting. Patients who can’t commit to the follow-up schedule. A stent left in for years causes more problems than it solved, and patients who can’t return for exchange every three to six months are often better managed with non-stenting strategies like enzyme replacement and pain management. You don’t want a stent placed because something can be stented. You want one placed because the alternative was worse. Read more on pancreatic stenting for how the procedure itself works once that decision has been made. Why choose Dr. Vipulroy Rathod for pancreatic stenting decisions? Dr. Vipulroy Rathod has been managing pancreatic ERCP and stenting decisions at Fortis Hospital Mulund for over three decades, with particular focus on chronic pancreatitis where the question of who benefits from stenting is harder than it looks. Many patients arrive having been told they need urgent stenting based on imaging alone, when a closer look at their symptoms and pain pattern suggests they don’t. Others arrive having been managed non-procedurally for years when a single well-timed stent would have changed their pain trajectory significantly. Knowing when not to stent is the harder skill. The procedure itself isn’t trivial, the complication rate isn’t zero, and the follow-up commitment is real. Patients who understand all of that before the first procedure tend to do better than those who weren’t told upfront. Book your consultation today with one of India’s most experienced specialists for pancreatic disease assessment and stenting decisions. Book Appointment Call now Frequently Asked Questions Does every chronic pancreatitis patient need a stent? No. Many are managed perfectly well with enzyme replacement, pain medication, and lifestyle changes. Stenting is reserved for patients with dominant strictures, recurrent pancreatitis, or pain not controlled by conservative measures. How urgently does a pancreatic stent need to be placed? It depends. Pancreatic duct leak after trauma needs urgent stenting within days. A dominant stricture causing chronic pain can be planned electively. Acute pancreatitis usually doesn’t need urgent stenting at all. Can a pancreatic stent be avoided with medication alone? For some patients yes, particularly those with milder duct changes and pain controlled by analgesia and enzyme replacement. For tight strictures causing recurrent pancreatitis, medication alone usually isn’t enough. Is stenting permanent? No. Plastic stents are exchanged every three to six months, and most patients eventually have them removed entirely once the underlying problem stabilises. Long-term stenting beyond a year or two is uncommon and usually means the underlying condition needs reassessment. Reference links- ERCP and Pancreatic Stenting Guidelines, American Society for Gastrointestinal Endoscopy — https://www.asge.org/home/practice-support/guidelines Chronic Pancreatitis Management Standards, World Gastroenterology Organisation — https://www.worldgastroenterology.org/guidelines  

When Is a Pancreatic Stent Needed? Read More »

What Is Pancreatic Stenting?

Pancreatic stenting is an endoscopic procedure used to keep the pancreatic duct open when something is blocking or narrowing it. A thin tube, usually plastic, sometimes metal, is placed inside the duct through ERCP. It restores drainage, brings down the pressure that builds up behind the obstruction, and usually relieves the pain that comes with it. Patients with chronic pancreatitis, duct stones, and certain pseudocysts are the typical candidates. So is a smaller group of pancreatic cancer patients whose duct gets compressed by the tumour. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “A stent isn’t a cure. It opens a blocked duct so the pancreas can drain. Whatever’s causing the blockage, a stone, a stricture, a tumour, still needs its own treatment. The stent buys time. It also buys relief from pain, which for these patients is often the biggest thing.” When pancreatic stenting is used? The decision to stent depends on what’s blocking the duct and how much trouble that blockage is causing. Pain, recurrent pancreatitis, jaundice from the same lesion, all of these factor in. Chronic pancreatitis with ductal strictures. Scar tissue inside the duct narrows it down, juices back up behind the narrowing, pressure rises, and pain follows. A stent across the stricture opens the channel again, and pain often eases significantly within days of placement. Pancreatic duct stones cause similar problems and stenting usually pairs with stone extraction. Stones come out first, sometimes with mechanical lithotripsy or extracorporeal shockwave lithotripsy assisting, then a stent holds the cleared duct open while inflammation settles. Pseudocyst drainage when communication exists. Some pseudocysts connect directly to the pancreatic duct, and a transpapillary stent lets the cyst drain naturally through the duodenum instead of needing percutaneous tubes hanging out of the abdomen. Prevention of post-ERCP pancreatitis. Brief. High-risk ERCP cases get a temporary 5 French stent placed at the end of the procedure. It drops the risk of post-procedure pancreatitis substantially in patients with normal anatomy undergoing therapeutic work, and the stent usually migrates out on its own within two to three weeks. A stent rarely solves the underlying problem on its own. Pancreatic stone extraction often happens during the same session, with stenting and stone removal addressing different ends of the same obstruction, the stone is the cause and the stent is what keeps things moving while everything heals. How the procedure works and what to expect? Pancreatic stenting is done under sedation through ERCP, similar setup to a routine bile duct procedure but technically harder. The pancreatic duct is smaller, narrower, less forgiving of guidewire manipulation. The scope used is a side-viewing duodenoscope, passed through the mouth into the second part of the duodenum. The opening of the pancreatic duct, the major papilla, is found and cannulated with a guidewire under fluoroscopy. If the stricture is tight, it gets dilated with a balloon. Then the stent slides over the wire into position. Total time, usually thirty to sixty minutes. If you’re the patient, here’s what that translates to. You’ll be asleep for the procedure. You’ll wake up sore in the throat. The next forty-eight hours can include mild abdominal pain, which is normal, but severe pain or fever is not and means going back to hospital. Most stents stay in for three to six months before exchange. Plastic stents are standard. Metal ones are used cautiously in pancreatic disease because they cause more long-term problems than they solve. Complications. Post-ERCP pancreatitis in about three to five percent. Stent migration, blockage, occasional duct injury. None of these are common, but they happen, and the people doing this work a lot see fewer of them than people doing it occasionally. Missed exchanges cause the worst problems. A stent left in too long blocks, blocked stents drive infection and pancreatitis, and a patient who was doing well for months can end up back in hospital because of a stent that should have been replaced. So the schedule matters as much as the placement itself. Read more on pancreatic stones and treatment for how stenting sits alongside stone extraction and shockwave lithotripsy in chronic pancreatitis management. Why choose Dr. Vipulroy Rathod for pancreatic stenting? Dr. Vipulroy Rathod has been performing pancreatic ERCP and stenting at Fortis Hospital Mulund for over three decades. Chronic pancreatitis strictures, duct stones, pseudocysts, the technically difficult cases where standard ERCP has failed and EUS-guided rendezvous becomes the way in. Pancreatic ERCP is harder than biliary, and the complication rate in inexperienced hands reflects that. A surprising number of patients arrive with stents placed years ago and then forgotten. The duct around them is now inflamed, the stent itself blocked, the patient has been having pain nobody connected back to the original procedure. A pancreatic stent works only if the person who placed it tracks it and removes it on time. Book your consultation today with one of India’s most experienced specialists for pancreatic stenting and chronic pancreatitis management. Book Appointment Call now Frequently Asked Questions How long does a pancreatic stent stay in? Usually three to six months before exchange. Is pancreatic stenting painful? The procedure itself isn’t, because it’s done under sedation. After. That’s where some patients have mild abdominal discomfort for a day or two, which is normal. What isn’t normal is severe pain or fever, those mean a complication and need urgent assessment. Most patients describe the actual recovery as easier than they expected, mostly throat soreness and a bit of tiredness, gone within twenty-four to forty-eight hours. Can pancreatic stents fall out on their own?  Yes, some are designed to. Short-duration prevention stents are made specifically to migrate out within two to three weeks without needing endoscopic removal. Other stents stay where placed until removed deliberately. What happens if a pancreatic stent gets blocked? A blocked stent causes the same problem the stent was placed to solve, plus infection on top. Pain returns, sometimes worse than before. Fever can develop. Pancreatitis episodes start happening. Urgent repeat ERCP to exchange the stent fixes

What Is Pancreatic Stenting? Read More »

EUS FNA vs EUS FNB: What Is the Difference?

EUS Fine Needle Aspiration (FNA) and EUS Fine Needle Biopsy (FNB) are both endoscopic ultrasound-guided sampling procedures used to obtain tissue from lesions in the pancreas, lymph nodes, and submucosal masses. The difference is in what each needle collects, FNA aspirates loose cells suspended in fluid for cytology, while FNB captures a small intact tissue core that preserves the lesion’s architecture for histology. Both share the same setup, the same scope, the same patient experience, but the diagnostic yield differs in important ways depending on what’s being sampled. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “FNA was the original technique and still works well for most pancreatic masses. FNB came later. The newer needle pulls actual tissue, not just cells, which matters for lymphomas, autoimmune disease, neuroendocrine tumours, anything where the cytologist needs to see how the cells are arranged, not just what they look like individually.” EUS-FNA vs EUS-FNB at a glance Factor EUS-FNA EUS-FNB Sample type Cells in fluid Tissue core Analysis Cytology Histology Passes needed Three to four One to two Best for Solid pancreatic mass Lymphoma, neuroendocrine ROSE dependency High Low How the two techniques differ? The needles themselves look similar from the outside, both pass through the same scope into the same target, both use the same ultrasound guidance. What changes is the tip design. FNA needle. A simple bevelled tip designed to aspirate cells and small fragments under suction. The sample comes out as a smear that’s spread on slides and stained for cytology. Multiple passes are usually needed, three or four, sometimes more if the cytopathologist isn’t on site to check adequacy in real time. FNB needles come in several designs, Franseen, fork-tip, reverse-bevel, all built to cut and retain a tissue core rather than just aspirate cells. One or two passes usually give enough tissue for histological analysis, which preserves the architecture of the lesion rather than just sampling individual cells. Diagnostic yield differs by target. For solid pancreatic adenocarcinoma, FNA and FNB perform similarly, both above ninety percent accuracy in expert hands. For lymphomas, gastrointestinal stromal tumours, autoimmune pancreatitis, and neuroendocrine tumours, FNB is meaningfully better because histology matters. Cost and availability also differ. FNA needles are cheaper and available in every endoscopy unit doing EUS. FNB needles cost more, aren’t stocked everywhere, and are sometimes used selectively rather than as the default. What separates a successful biopsy from a non-diagnostic one is matching the technique to the lesion. Endoscopic ultrasound services that have both FNA and FNB available let the operator choose mid-procedure based on what the lesion looks like, rather than committing to one approach before the scope is even passed. When each technique is preferred? The choice isn’t always either-or. Many cases get FNA first, with FNB held in reserve if the initial passes are non-diagnostic. Solid pancreatic mass, likely adenocarcinoma. FNA is usually enough. Pancreatic cancer cells are recognisable on cytology, and the architecture matters less for diagnosis. ROSE confirms adequacy before the patient leaves the procedure room. For suspected lymphoma anywhere, FNB is preferred from the start. Lymphoma diagnosis needs flow cytometry, immunohistochemistry, and architectural assessment, none of which a cell aspirate can provide reliably. Going straight to FNB saves a repeat procedure. Subepithelial GI tumours. Stromal tumours, leiomyomas, schwannomas. These need histology and immunohistochemistry to differentiate. FNB is the default. Autoimmune pancreatitis is another situation where FNB matters. The diagnosis depends on seeing characteristic inflammatory patterns in the tissue, lymphoplasmacytic infiltrate, storiform fibrosis, obliterative phlebitis. None of these can be picked up reliably on FNA cytology. So the decision often gets made in the procedure room itself, based on what the ultrasound is showing. Read more on pancreatic cancer detection to understand how the choice of biopsy technique fits into the broader workup of suspected pancreatic disease. Why choose Dr. Vipulroy Rathod for EUS biopsy? Dr. Vipulroy Rathod has been performing EUS-guided tissue sampling at Fortis Hospital Mulund since the technique first arrived in India, with experience covering both FNA and the newer FNB needles as they became available over the years. Over three decades of pancreatic masses, lymph node staging, cystic lesion analysis, and the case-by-case judgment that decides which needle gets used. The needle choice matters more than patients usually realise. Wrong technique on the wrong lesion produces a non-diagnostic biopsy, which means a repeat procedure, more sedation, more delay. Right technique on the first attempt avoids that whole detour. Book your consultation today with one of India’s most experienced endosonographers for EUS-guided biopsy and pancreatic disease assessment. Book Appointment Call now Frequently Asked Questions Is EUS-FNB more accurate than EUS-FNA? For most solid pancreatic masses, accuracy is similar between the two. For lymphomas, neuroendocrine tumours, GI stromal tumours, and autoimmune pancreatitis, FNB is meaningfully better because the diagnosis needs histology rather than cytology alone. Does the patient experience differ between FNA and FNB? No. The procedure feels the same from the patient’s side. Same sedation, same scope, same recovery time. The difference is in the needle tip and what comes out at the end. Can FNA and FNB be done in the same session? Yes, often. Many operators start with FNA, check adequacy with ROSE if available, and switch to FNB if the initial passes don’t give enough material. Both needles fit through the same scope. Why isn’t FNB used for everything? Cost, availability, and the fact that FNA still works well for the most common indication, solid pancreatic adenocarcinoma. In centres where both are available, FNB use has been steadily rising for lesions where histology matters. Reference links- EUS-Guided Tissue Acquisition Guidelines, American Society for Gastrointestinal Endoscopy — https://www.asge.org/home/practice-support/guidelines Endoscopic Ultrasound in Pancreatic Disease, World Gastroenterology Organisation — https://www.worldgastroenterology.org/guideline  

EUS FNA vs EUS FNB: What Is the Difference? Read More »

What Is EUS Fine Needle Aspiration (FNA)?

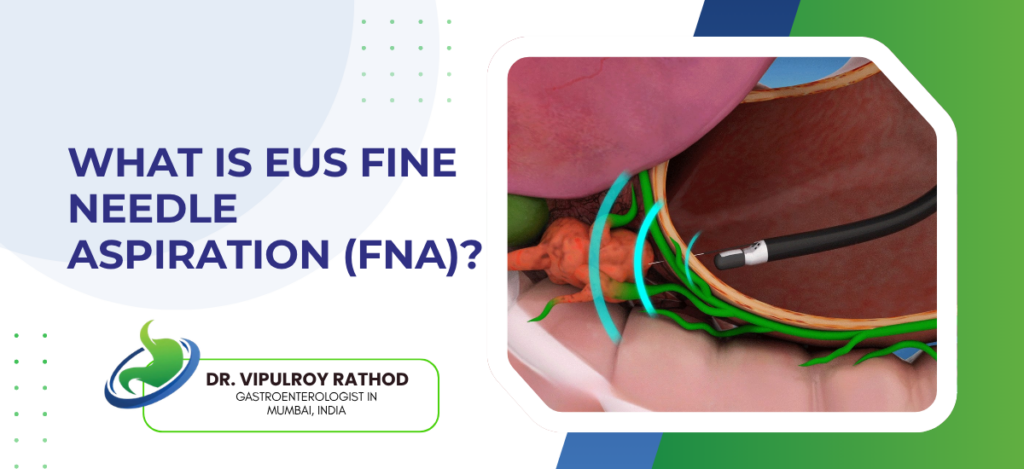
EUS Fine Needle Aspiration (EUS-FNA) is a minimally invasive biopsy procedure that combines endoscopic ultrasound with a thin needle to sample tissue from organs deep inside the abdomen and chest. It is the standard method for getting a definitive diagnosis from pancreatic lesions, lymph nodes, the bile duct wall, and submucosal masses in the GI tract. The whole thing happens through a scope passed down the mouth, no incisions, usually under sedation. For most pancreatic cancers, EUS-FNA is what confirms the diagnosis before any treatment decision gets made. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “EUS-FNA changed how we diagnose pancreatic disease. Before it existed, patients went straight to surgery on the basis of a CT scan. Now we sample the lesion first. The biopsy answers the question. Sometimes it isn’t cancer at all, and we’ve saved someone from a major operation they never needed.” What EUS-FNA is used for? The procedure is built around one capability, getting tissue from places that are hard to reach any other way. The pancreas sits behind the stomach, deep in the abdomen, and is impossible to biopsy through the skin in most cases without risk. Pancreatic masses. The classic indication. Any solid lesion in the pancreas needing histological confirmation before treatment planning. The needle goes through the stomach or duodenum wall directly into the pancreas, real-time ultrasound guidance the whole way. Lymph node sampling for staging in cancers of the oesophagus, lung, pancreas, and stomach. Knowing whether nearby nodes are involved changes the surgical plan, sometimes pulls a case from operable to inoperable. Cystic lesions of the pancreas. Fluid aspirated from a pancreatic cyst is sent for cytology, CEA, glucose, and now molecular markers. This is what tells the difference between a benign serous cyst and a mucinous one with cancer potential. Submucosal tumours of the stomach and oesophagus. These sit beneath the lining and can’t be reached with a regular biopsy through a standard endoscope. EUS-FNA goes through the wall and samples them directly. The diagnostic yield depends on the operator, the needle, and the on-site cytology setup. Endoscopic ultrasound services that have a cytopathologist available during the procedure consistently produce better samples, because the operator gets immediate feedback on whether the tissue is adequate or another pass is needed. How EUS-FNA is performed? The procedure itself is quick, usually thirty to forty minutes from start to finish, and patients go home the same day in most cases. A linear-array echoendoscope is passed through the mouth and positioned in the stomach or duodenum, depending on which organ is being sampled. The ultrasound at the tip of the scope locates the lesion, the operator measures it, and a fine needle, usually 22 or 25 gauge, is advanced through the scope and into the target under continuous ultrasound guidance. Multiple passes. Two to four passes through the lesion are standard, each pass collecting tissue into a syringe attached to the needle hub. The cytopathologist examines the smears in real time when ROSE (rapid on-site evaluation) is available. Most patients receive deep sedation rather than general anaesthesia. Recovery is short, an hour or two in the day-care unit, and the patient usually goes home by evening. Complications are rare. Bleeding, pancreatitis, and infection occur in well under one percent of cases in experienced hands. Tumour seeding along the needle tract is theoretically possible but extremely uncommon in pancreatic FNA. Results take three to five working days, sometimes faster if ROSE was used during the procedure to confirm adequacy. The accuracy of EUS-FNA in pancreatic masses runs above ninety percent in expert centres, which is why it has become the standard step before any pancreatic surgery is scheduled. Read more on pancreatic cancer detection for how EUS-FNA fits into the broader workup of suspected pancreatic disease. Why choose Dr. Vipulroy Rathod for EUS-FNA? Dr. Vipulroy Rathod has been performing EUS-FNA at Fortis Hospital Mulund since the technique first became available in India in the late 1990s, which makes him one of the earliest endosonographers in the country to adopt it. Over thirty years of pancreatic biopsies, lymph node staging, cystic lesion characterisation, and the careful technique that makes each pass count. What separates a good EUS-FNA from a poor one isn’t the equipment, it’s the operator. The choice of needle, the angle of approach, the number of passes, the handling of the specimen, all of these affect whether the cytopathologist gets enough tissue to give a definitive answer. Volume teaches that part of the work. Book your consultation today with one of India’s most experienced endosonographers for EUS-FNA and pancreatic disease assessment. Book Appointment Call now Frequently Asked Questions Is EUS-FNA painful? No, the procedure is done under sedation and patients don’t feel it. Mild throat soreness for a day afterwards is common, but most patients are eating normally by evening. How accurate is EUS-FNA for pancreatic cancer? In experienced hands, diagnostic accuracy for pancreatic masses runs above ninety percent. False negatives can occur in small or fibrotic tumours, which is why a single negative biopsy doesn’t always rule out cancer if the imaging looks suspicious. How long does EUS-FNA take? The procedure itself is usually thirty to forty minutes. Including sedation recovery, most patients are in the day-care unit for three to four hours before going home. Can EUS-FNA spread cancer? The theoretical risk of tumour seeding along the needle tract exists but is extremely rare in pancreatic FNA. For lesions that will be surgically resected, the needle tract is included in the resection specimen, eliminating any residual risk. Reference links- EUS-Guided Tissue Acquisition Guidelines, American Society for Gastrointestinal Endoscopy — https://www.asge.org/home/practice-support/guidelines Endoscopic Ultrasound in Pancreatic Disease, World Gastroenterology Organisation — https://www.worldgastroenterology.org/guidelines

What Is EUS Fine Needle Aspiration (FNA)? Read More »

Whipple Surgery vs Endoscopic Treatment

Whipple surgery and endoscopic treatment are two different categories of intervention in pancreatic and biliary disease. Whipple is a major open operation that removes the head of the pancreas with curative intent in resectable cancer. Endoscopic treatment is a group of minimally invasive scope-based procedures used for biopsy, biliary drainage, pain management, and palliation. The two aren’t alternatives. They handle different parts of the same pathway. The mistake patients make is treating them as competing options. According to Dr. Vipulroy Rathod,Gastroenterologist in Mumbai, “Patients walk in hoping endoscopy can replace the Whipple. For resectable cancer it can’t. What endoscopy does well is everything around the operation. Biopsy. Drainage. Pain control. Without that work, the Whipple doesn’t go well, and for patients who aren’t surgical candidates, endoscopy is the entire treatment.” Whipple vs endoscopic treatment at a glance Factor Whipple Surgery Endoscopic Treatment Approach Major open surgery Through a scope Intent Curative removal Staging or palliation Recovery Three to four weeks One to two days Anaesthesia General, prolonged Sedation, short Use in cancer Resectable disease only Almost all stages   When Whipple is the right choice? Whipple is considered only when two conditions are met. The tumour can be removed in one piece. The patient is fit enough to recover. Resectable pancreatic head cancer. A tumour confined to the head of the pancreas without major vessel involvement. Removed together with surrounding lymph nodes so the pathologist can stage it properly. Periampullary tumours qualify for the same operation. Cancers of the ampulla of Vater, distal bile duct, and duodenum next to the pancreas. Outcomes are often noticeably better than for pancreatic adenocarcinoma itself. Neuroendocrine tumours and premalignant IPMNs. Selected cases with high-risk features go to Whipple. Less common, but the operation is the same and the indication is clear when histology supports it. After successful neoadjuvant chemotherapy. Borderline resectable cases that converted with chemotherapy are taken to Whipple once restaging confirms the tumour has pulled back from vessels. Where Whipple doesn’t belong matters as much. Pancreatic cancer treatment planning excludes Whipple in locally advanced disease, in metastatic cancer, and in patients whose general condition makes recovery unrealistic. Sending the wrong patient into theatre causes more harm than the cancer would in the same period. Where endoscopic treatment fits? Endoscopy isn’t a competitor to Whipple. It’s the work that surrounds it. Diagnosis, drainage, pain management, complication handling. EUS-guided biopsy. Every reasonable pancreatic cancer plan starts here. Tissue from the tumour with millimetre accuracy. Histology decides the regimen, the timing, and whether surgery is even appropriate. ERCP with biliary stenting handles the jaundice that pancreatic head tumours cause. Often the first procedure done after diagnosis, well before any conversation about Whipple is finalised. ERCP after Whipple. Anastomotic strictures, bile leaks, recurrent stones in the reconstructed plumbing. Problems that would otherwise mean repeat open surgery, fixed through a scope instead. EUS-guided celiac plexus block for pain control in unresectable disease. Durable relief, often months at a time, without escalating opioid doses indefinitely. The two approaches work together in modern pancreatic cancer care, not against each other. Read more on pancreatic cancer detection to see how endoscopy fits into the broader pathway, why it usually comes first, and why so many patients are past the Whipple option by the time they’re diagnosed. Why choose Dr. Vipulroy Rathod for pancreatic disease management? Dr. Vipulroy Rathod has been doing advanced endoscopic work in pancreatic and biliary disease at Fortis Hospital Mulund since the late 1990s, with EUS-guided biopsy, ERCP, celiac plexus block, and the staging assessment that decides whether Whipple is the right next step at all. Volume that few centres in India match. The harder skill in pancreatic disease isn’t doing either procedure well. It’s the sorting. Which patient belongs in which corridor, with which preparation, at which week. Multidisciplinary discussion with surgeons and oncologists is where that gets worked out, not in a single specialist’s clinic in isolation. Book your consultation today with one of India’s most experienced specialists for pancreatic disease assessment and treatment planning. Book Appointment Call now Frequently Asked Questions Can endoscopic treatment replace Whipple surgery? Not for resectable cancer. What is the recovery time after Whipple surgery? Seven to ten days in hospital, three to four weeks at home before normal activity. Full recovery runs two to three months. Is endoscopic treatment safer than Whipple surgery? Safer in immediate complication terms, but the two aren’t trying to do the same thing. Endoscopy can’t cure resectable cancer. Can the Whipple operation be done laparoscopically or robotically? Yes, in selected centres with surgeons trained in minimally invasive pancreatic surgery, with outcomes comparable to open Whipple in expert hands. Reference links- Pancreatic Adenocarcinoma Guidelines, National Comprehensive Cancer Network — https://www.nccn.org/guidelines/guidelines-detail?category=1&id=1455 Therapeutic Endoscopy in Pancreatic Disease, American Society for Gastrointestinal Endoscopy — https://www.asge.org/home/practice-support/guidelines

Whipple Surgery vs Endoscopic Treatment Read More »

What Is Borderline Resectable Pancreatic Cancer?

Borderline resectable pancreatic cancer (BRPC) is a stage where the tumour involves nearby blood vessels, making complete surgical removal (R0 resection) difficult or high-risk, though still technically possible. It lies between resectable and locally advanced disease, requiring multidisciplinary care, usually starting with neoadjuvant therapy (chemotherapy or radiation) to reduce tumour size. Around fifteen to twenty percent of pancreatic cancer diagnoses fall into this category, and accurate staging within the first few weeks decides whether conversion to resectable disease is realistic. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Borderline resectable is the category where the most damage gets done by rushing, patients pushed straight to surgery without neoadjuvant therapy often end up with positive margins or abandoned operations, and the ones given proper chemotherapy first frequently come back resectable a few months later with much better outcomes.” How borderline resectable disease is defined? It’s defined by the imaging, not by how the patient feels. A radiologist trained in pancreatic imaging looks at exactly how the tumour relates to four key vessels. Portal vein and superior mesenteric vein contact. Up to 180 degrees of contact, or short-segment occlusion that’s reconstructible, still keeps a case borderline rather than locally advanced. The vein is forgiving, surgeons can rebuild it if needed. Superior mesenteric artery involvement. Less than 180 degrees of contact is the threshold. Anything more than that pushes the case into locally advanced territory, where surgery isn’t appropriate anymore. The celiac axis and hepatic artery get measured the same way. Limited contact under 180 degrees keeps the case in borderline category, with the option of reconstruction during surgery if needed. Distant spread on imaging. Even small liver lesions or peritoneal deposits change the classification entirely. The cancer is no longer borderline, it’s metastatic, and the treatment route shifts to systemic chemotherapy. The classification isn’t a judgment call, it’s a measurement, and the measurement is what dictates the next step. Pancreatic cancer treatment planning at this point almost always starts with EUS-guided biopsy to confirm the histology before any chemotherapy begins, because the regimen choice depends on knowing exactly what the tumour is. How borderline cases are actually treated ? The standard approach now is chemotherapy first, surgery second, in patients who respond well enough to make resection worthwhile. The reasoning behind this shift has played out across multiple trials over the last decade. Neoadjuvant chemotherapy as the opening move. FOLFIRINOX is the most common regimen in fit patients, three to six months of it, followed by a restaging CT to see how the tumour has responded. Gemcitabine-based combinations are used in patients who can’t tolerate FOLFIRINOX. Restaging and decision-making. If the tumour has pulled back from the vessel and there’s no new disease elsewhere, surgery is on the table. If it hasn’t responded or has grown, the case is reclassified and the treatment plan changes entirely. Surgery, when it happens, is technically demanding. A Whipple procedure or distal pancreatectomy with possible vascular reconstruction, often three to four week recovery, and adjuvant chemotherapy afterwards is almost always recommended. What happens if conversion fails. Some borderline tumours don’t shrink, some grow despite chemotherapy, and these patients move into the locally advanced or metastatic category. Treatment then becomes about durable disease control rather than cure. The reason borderline resectable disease is its own category is because it behaves differently from both resectable and unresectable cancer. Read more on resectable vs unresectable pancreatic cancer to see how the staging logic separates these groups and why the treatment paths diverge so sharply. Why choose Dr. Vipulroy Rathod for borderline pancreatic cancer assessment? Dr. Vipulroy Rathod has been involved in the imaging review and EUS-based assessment of borderline pancreatic cancers at Fortis Hospital Mulund for over three decades. Many patients arrive having been told surgery is the next step, when a closer look at vessel involvement shows the case should have gone for neoadjuvant therapy first. The reverse also happens, patients told nothing can be done when the imaging actually puts them firmly in borderline territory with a real chance of conversion. The borderline category is where careful staging matters most. Push a patient into surgery too early and the operation gets abandoned. Wait too long without giving chemotherapy a real trial and the window closes. Both errors are avoidable with proper imaging review and EUS confirmation upfront. Book your consultation today with one of India’s most experienced specialists for borderline pancreatic cancer staging and treatment planning. Book Appointment Call now Frequently Asked Questions Can borderline resectable pancreatic cancer be cured? Yes, when the tumour responds well to neoadjuvant chemotherapy and successful surgery follows. Cure rates are lower than in fully resectable disease but meaningfully higher than in locally advanced cases, particularly when adjuvant chemotherapy is given afterwards. How long does chemotherapy last before surgery? Typically three to six months of FOLFIRINOX or a gemcitabine-based regimen, followed by a restaging scan. The exact duration depends on tolerance, response on imaging, and surgeon preference at the centre managing the case. What happens if borderline cancer doesn’t respond to chemotherapy? The case gets reclassified, usually as locally advanced. Surgery is taken off the table and treatment shifts to continued systemic therapy with or without radiation, focused on controlling the disease rather than removing it. Is borderline resectable pancreatic cancer the same as locally advanced? No. Borderline cases have limited vessel involvement that’s potentially reversible with chemotherapy, while locally advanced cases have arterial encasement that can’t be reconstructed even after good response. The distinction changes everything about prognosis and treatment options. Reference links- Pancreatic Adenocarcinoma Guidelines, National Comprehensive Cancer Network — https://www.nccn.org/guidelines/guidelines-detail?category=1&id=1455 Borderline Resectable Pancreatic Cancer Consensus, International Study Group of Pancreatic Surgery — https://www.surgjournal.com/article/S0039-6060(14)00227-5/fulltext

What Is Borderline Resectable Pancreatic Cancer? Read More »

Resectable vs Unresectable Pancreatic Cancer

Resectable pancreatic cancer is the kind that can be surgically removed with a reasonable shot at cure. Unresectable means the tumour has grown into or wrapped around structures that no surgeon can safely take out. The line between the two is drawn on imaging, almost always a contrast-enhanced CT, and that line decides what the next year of treatment looks like. Only about one in five patients are resectable when they’re first diagnosed, which is partly why this disease still has such a bad reputation. A Gastroenterologist in Mumbai seeing these cases spends most of the first visit working out which category the patient falls into. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Patients are sometimes told their pancreatic cancer is operable when the imaging actually shows borderline involvement of a major vessel, and they end up in surgery that gets abandoned mid-procedure, which is the worst possible outcome and almost always preventable with proper staging upfront.” Resectable vs unresectable pancreatic cancer at a glance Factor Resectable Unresectable Vessel involvement No major contact Encases major artery Treatment intent Curative surgery Disease control only First-line approach Surgery upfront Chemotherapy first Five-year survival Twenty to thirty percent Under five percent Cases at diagnosis Fifteen to twenty percent Majority of patients   What separates resectable from unresectable disease ? It’s all about anatomy. Specifically, where the tumour sits in relation to the big vessels around the pancreas. Resectable. Tumour is in the pancreas, isn’t touching the superior mesenteric artery, celiac axis, or hepatic artery, and any contact with the portal or superior mesenteric vein is small enough to be reconstructed. Surgery here is being done with cure in mind. Borderline resectable. There’s some vessel contact, but not enough to rule surgery out. These cases almost always start with chemotherapy first, usually FOLFIRINOX or a gemcitabine combination, and the goal is to pull the tumour back from the vessel before anyone takes a scalpel to it. Locally advanced disease is a different conversation entirely. The artery is encased, the vessel can’t be reconstructed, and any surgeon attempting resection would do more harm than the cancer itself. Treatment becomes systemic chemotherapy with or without radiation. Metastatic. Once the cancer has reached the liver, the peritoneum, the lungs, or distant lymph nodes, surgery is off the table regardless of what the primary looks like. Chemotherapy now is about controlling progression and managing symptoms, not removing anything. The classification isn’t a footnote in the report, it’s the single decision that drives everything that follows. Pancreatic cancer treatment routes from this point on, whether neoadjuvant chemotherapy, surgery, or palliation, all rest on getting this initial reading right, which often means a second pair of trained eyes on the imaging and EUS for tissue confirmation. What changes between the two pathways ? Once the category is set, the treatment route diverges sharply. Patients should know what each path actually looks like before agreeing to it. Surgery upfront for resectable cases. A Whipple procedure for head-of-pancreas tumours, distal pancreatectomy for body and tail. Both are major operations and recovery is at least three to four weeks. Five-year survival sits between twenty and thirty percent with surgery alone, better when adjuvant chemotherapy is added. For borderline cases, chemotherapy comes first. Three to six months of FOLFIRINOX or a similar regimen, then a restaging scan to see what’s happened. If the tumour has pulled back, surgery becomes possible. If not, the chemo response itself tells you something about the biology. Definitive chemoradiation for locally advanced disease. No operation, but aggressive systemic and local treatment can shrink the cancer, ease symptoms, and occasionally bring a patient back into resectable territory. Most of the time the goal is durable disease control. Palliative care for metastatic disease. Chemotherapy to slow progression, biliary stenting if jaundice develops, EUS-guided celiac plexus block for pain, and frank conversations about prognosis from the first consultation onwards. Where a patient ends up depends entirely on how accurately the initial staging is done, which is why second opinions before any locked-in decision are common and reasonable. Read more on pancreatic cancer detection to understand why most of these cases are already past resectable by the time they’re picked up. Why choose Dr. Vipulroy Rathod for pancreatic cancer assessment? Dr. Vipulroy Rathod has been involved in staging and endoscopic assessment of pancreatic cancer at Fortis Hospital Mulund for over thirty years, with a particular focus on EUS-guided biopsy and the careful imaging review that decides resectability. Many of the patients we see arrive with a CT report calling their cancer operable, when a closer look at the vessel involvement tells a quite different story. Re-reading the scan properly often saves a patient from a surgery that was never going to succeed. The first few decisions in pancreatic cancer are the most consequential. Get the staging right and the rest of the plan follows logically. Get it wrong and the patient loses months on the wrong pathway, which in this disease is time nobody has. Book your consultation today with one of India’s most experienced specialists for pancreatic cancer staging and treatment planning. Book Appointment Call now Frequently Asked Questions How is resectability decided in pancreatic cancer? A contrast-enhanced CT looks at how the tumour sits in relation to the superior mesenteric artery, celiac axis, hepatic artery, and portal vein. There are specific criteria around degree of vessel contact that define each category, and the imaging is usually reviewed by both a radiologist and a surgical team before the final call is made. Can borderline resectable pancreatic cancer become resectable? Yes, and this happens often enough to be worth attempting. Neoadjuvant chemotherapy, sometimes paired with radiation, can shrink the tumour back from the involved vessel, and a restaging scan a few months later tells you whether resection is now safe. Is unresectable pancreatic cancer treatable? Treatable yes, curable usually not. Chemotherapy and radiation can control the disease for a meaningful period, manage symptoms, and extend survival. A small group of patients

Resectable vs Unresectable Pancreatic Cancer Read More »

Which Pancreatic Cysts Turn Cancerous?

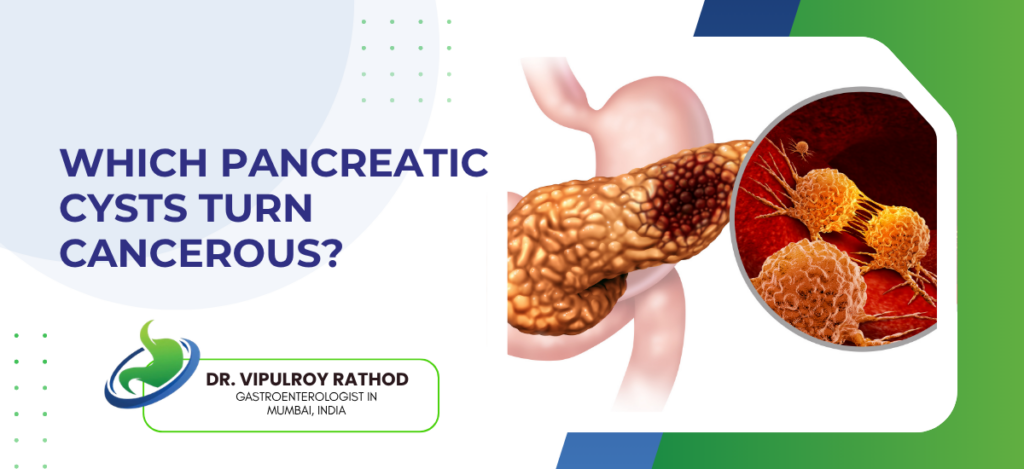
Most pancreatic cysts are harmless, the trouble is that a small but real proportion aren’t, and telling them apart on imaging alone is one of the harder calls in GI medicine. Roughly one in fifteen cysts picked up incidentally on a scan has malignant potential, and another small group are already early cancers by the time they’re found. The type of cyst matters far more than the size, although both factor into the decision. Any Gastroenterologist in Mumbai who sees these regularly will tell you the worst mistake is assuming a cyst is benign without proper characterisation. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Patients are often told their pancreatic cyst is nothing to worry about because it’s small, but size alone is a poor predictor, mucinous cysts of two centimetres can still progress to cancer while serous cysts of seven centimetres almost never do, and the only way to know which one you’re dealing with is proper EUS evaluation with fluid analysis.” The pancreatic cyst types and their cancer risk Not all cysts behave the same way, and grouping them is what the entire workup hinges on. Serous cystadenoma. Almost always benign, the cancer risk is well under one percent. These are usually small, multi-loculated, and look like a honeycomb on imaging. Most can be watched and never need anything done. Mucinous cystic neoplasm, MCN. Found mostly in middle-aged women, in the body or tail of the pancreas. These do have malignant potential, around ten to fifteen percent harbour cancer at the time of surgery, and the consensus is that most should be resected once identified. Intraductal papillary mucinous neoplasm, IPMN. The most common cyst with cancer potential, and the most complicated to manage. Risk depends on subtype: main-duct IPMN carries a high risk of malignancy, around forty to seventy percent, while branch-duct IPMN sits at a much lower five to fifteen percent unless worrisome features develop. Solid pseudopapillary neoplasm. Rare, mostly in young women, low but real malignant potential. Usually treated with surgical resection because of the long lifespan ahead of the patient. Pseudocysts. Not true neoplasms, these form after pancreatitis and don’t turn cancerous. They can mimic cystic tumours on imaging though, which is why fluid analysis matters. The decision between watch-and-wait and surgical resection comes down to which type is sitting in front of you. Endoscopic ultrasound with fine-needle aspiration is the test that pulls fluid for cytology, CEA, glucose, and now molecular markers, all of which sharpen the diagnosis considerably beyond what a CT or MRI alone can say. Worrisome features that change the management Even within a cyst type, certain findings raise the concern level enough to move a case from surveillance into the operating theatre. Size above three centimetres in a branch-duct IPMN, especially with growth on follow-up scans. Steady growth is sometimes more concerning than the absolute number. A mural nodule or solid component inside the cyst on imaging. This is the single most worrying finding because it often correlates with high-grade dysplasia or invasive cancer. Main pancreatic duct dilation above five millimetres, particularly with cyst communication. This shifts the diagnosis towards main-duct or mixed IPMN, which carries the highest malignant risk. Jaundice, new-onset diabetes, or unexplained weight loss alongside the cyst. These are clinical red flags that the cyst may already be doing something it shouldn’t. Cyst fluid markers. High CEA suggests mucinous, low glucose suggests mucinous, and the newer KRAS and GNAS mutation testing has improved diagnostic accuracy significantly over the last few years. Worrisome features don’t always mean cancer, but they almost always mean the patient needs closer evaluation rather than a routine yearly scan. Read more on pancreatic cancer vs pancreatic cyst for how the distinction is drawn in cases where imaging alone leaves the question open. Why choose Dr. Vipulroy Rathod for pancreatic cyst assessment ? Dr. Vipulroy Rathod has been performing EUS-guided assessment of pancreatic cysts at Fortis Hospital Mulund since the late 1990s, which puts him among the earliest endosonographers in India to characterise these lesions properly. Many of the patients we see have been told their cyst is benign on the basis of a CT scan alone, which is exactly the kind of incomplete workup that misses the cases that needed earlier surgical referral. The judgment call on a pancreatic cyst sits between two errors. Over-treat a benign serous cystadenoma and the patient gets unnecessary surgery on a notoriously difficult organ. Under-treat a main-duct IPMN and the patient comes back two years later with pancreatic cancer. Volume and proper EUS technique are what keep both errors rare. Book your consultation today with one of India’s most experienced specialists for pancreatic cyst characterisation and surveillance planning. Book Appointment Call now Frequently Asked Questions Are all pancreatic cysts cancerous? No, most are benign. The ones with malignant potential are mainly mucinous cystic neoplasms and intraductal papillary mucinous neoplasms, and even within those groups not every cyst becomes cancer. How often should pancreatic cysts be monitored? Surveillance intervals depend on the type, size, and worrisome features. Small branch-duct IPMNs without concerning features are often watched every six to twelve months, while larger or more complex cysts may need imaging every three to six months. Can pancreatic cysts be removed without surgery? Surgical resection remains the standard for cysts with high cancer risk. Some experimental endoscopic ablation techniques exist for specific cyst types, but they aren’t yet routine and aren’t appropriate for cysts already showing worrisome features. Do pancreatic cysts cause symptoms? Most are silent and found incidentally on scans done for other reasons. Larger ones can cause abdominal pain, back pain, or jaundice if they press on nearby structures, and new-onset diabetes or weight loss in someone with a known cyst is always a warning sign. Reference links- Pancreatic Cyst Management Guidelines, American Gastroenterological Association — https://gastro.org/clinical-guidance/asymptomatic-neoplastic-pancreatic-cysts/ IPMN and Mucinous Cyst Consensus Recommendations, International Association of Pancreatology — https://pancreapedia.org/reviews/international-consensus-fukuoka-guidelines-for-management-of-ipmn-and-mcn-of-pancreas

Which Pancreatic Cysts Turn Cancerous? Read More »

What Is Walled-Off Pancreatic Necrosis?

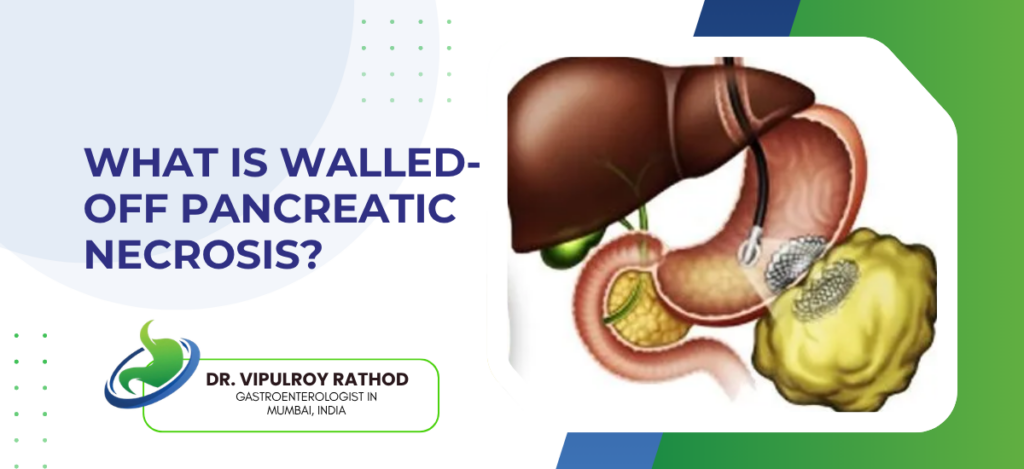
Walled-off pancreatic necrosis, or WON, is what dead pancreatic tissue becomes once the body has had four to six weeks to build a thick capsule around it. Before that wall forms, the dead area is loose, soft, and unsafe to touch. After the wall forms, it can be drained, accessed, and eventually cleared out without open surgery. Most patients reach this stage after a severe episode of acute pancreatitis with necrosis, and timing matters more here than in almost any other GI condition a Gastroenterologist in Mumbai deals with. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “WON is one of the few situations in gastroenterology where waiting is the right thing to do, the cavity has to mature before drainage is safe, and patients who get rushed into procedures during the first three weeks usually end up worse than the ones who were watched carefully and treated at the right time.” How walled-off necrosis forms and how it gets diagnosed? The wall doesn’t appear overnight, it’s the body doing slow inflammatory work, and recognising the stage on imaging is what tells the treating doctor whether to act or to keep waiting. The dying phase, week one to two. Severe acute pancreatitis kills off sections of the pancreas and the fat surrounding it. At this stage there’s no capsule, just necrotic tissue mixed with fluid sitting in the upper abdomen. Inflammation and demarcation, week three to four. The body starts forming a fibrous reaction around the dead area. The contents stay messy, partly solid, partly liquid, but a boundary begins to appear on CT. Walled-off stage, after week four. A thick non-epithelial wall now contains the necrosis. This is the point at which the lesion gets formally called WON, and it’s the point at which endoscopic drainage actually becomes a reasonable option. Imaging confirmation. Contrast-enhanced CT or MRI is the test of choice, both to confirm wall maturity and to see whether infection, gas bubbles, or new fluid pockets have developed alongside. Reading the imaging right is half the management. Once a mature wall is confirmed and the patient has symptoms, pancreatic stone extraction and EUS-guided cavity drainage can be planned safely, often as the same procedure if the anatomy allows How walled-off necrosis is treated, step by step? Not every WON needs intervention. Some shrink on their own once the wall has matured fully, the body absorbs the contents over months, and the patient never needs a procedure. The ones that do need treatment usually announce themselves through symptoms or infection. Watch and wait when the patient is well, the cavity is small, and there’s no infection. Repeat scans every few weeks, monitor for fever or weight loss, intervene only if something changes. EUS-guided drainage for symptomatic or infected collections. A stent, often a lumen-apposing metal stent, is placed through the stomach or duodenum directly into the cavity under ultrasound guidance. Fluid drains out, the cavity starts to collapse. Direct endoscopic necrosectomy. Once a stent is in place, the same opening can be used in follow-up sessions to enter the cavity with a scope and physically remove dead tissue. This is repeated, sometimes five or six times, until the cavity is clean. Stent removal and follow-up. When the cavity has shrunk and there’s no more debris, the stent comes out. Imaging at three and six months confirms the cavity has closed. The hardest part for patients is accepting that treatment isn’t one event, it’s a sequence. Read more on pancreatic necrosis treatment for how the step-up approach plays out across multiple sessions in real cases. Why choose Dr. Vipulroy Rathod for walled-off necrosis management ? Dr. Vipulroy Rathod has been managing walled-off necrosis at Fortis Hospital Mulund for over three decades, including some of the earliest EUS-guided drainage cases performed in India. Many of the patients we see arrive after weeks of antibiotics elsewhere, with collections that should have been drained sooner or, occasionally, ones that were touched too early and made worse. Getting WON right is mostly about timing and access. The procedure itself is technically demanding, but the bigger judgment call is choosing the right week to intervene and the right route into the cavity. Both come with volume. Book your consultation today with one of India’s most experienced specialists for walled-off pancreatic necrosis assessment and endoscopic drainage. Book Appointment Call now Frequently Asked Questions How long does walled-off pancreatic necrosis take to form? A mature wall usually takes four to six weeks after the original episode of acute pancreatitis. Before this window, the collection is called acute necrotic collection, not WON, and it isn’t safe to drain. Can walled-off necrosis resolve on its own? Smaller, sterile, asymptomatic collections often shrink and get absorbed over several months without any intervention. Larger ones, infected ones, or any that cause pain, fever, or pressure on nearby organs do need drainage. Is endoscopic drainage of WON painful? The procedure is done under sedation or general anaesthesia and patients don’t feel it. There can be some abdominal discomfort for a day or two afterwards, but most patients are eating and moving within twenty-four hours. What happens if walled-off necrosis is left untreated? If it stays sterile and small, sometimes nothing. If it gets infected or grows large, it can cause sepsis, compress the bile duct or stomach outlet, bleed, or perforate. These complications are why most symptomatic cases need active management. Reference links- Acute Pancreatitis Management Guidelines, American College of Gastroenterology — https://gi.org/guideline/acute-pancreatitis/ Necrotising Pancreatitis Treatment Standards, World Gastroenterology Organisation — https://www.worldgastroenterology.org/guidelines/acute-pancreatitis/acute-pancreatitis-english

What Is Walled-Off Pancreatic Necrosis? Read More »

Scroll to Top
Call Now Button