...

Dr. Vipulroy Rathod

Blog

Your blog category

How Does Third Space Endoscopy Treat Complex GI Conditions

Third Space Endoscopy: Treating Complex GI Conditions From Inside the Gut Wall

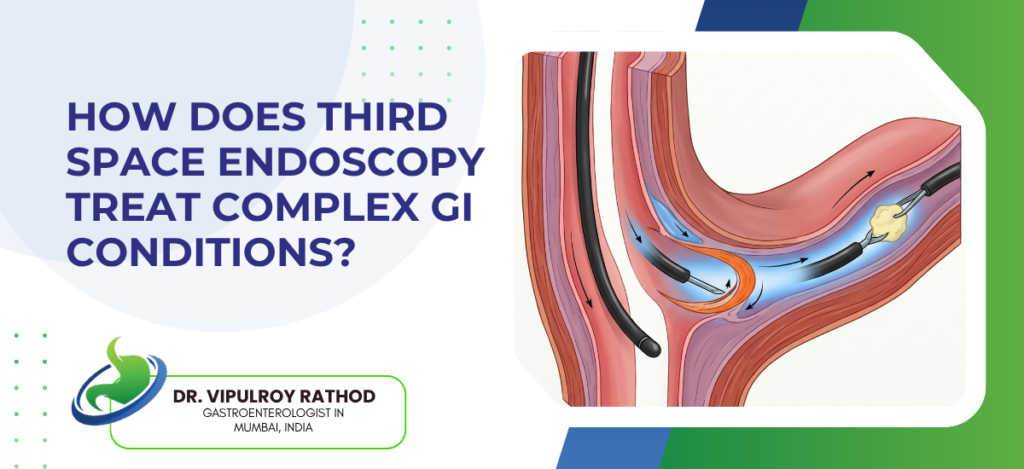
It works from inside the gut wall. Between the inner lining and the outer muscle lies a thin submucosal layer, and the endoscope can open a tunnel in that space and work there. Passed through the mouth or the anus, it lets the doctor cut a tight muscle, remove a tumour or divide a pouch without a single cut on the skin. Third space endoscopy now offers an option for problems that once meant surgery. According to Dr. Vipulroy Rathod, Gastroenterology Specialist in Mumbai, “What I value in third space work is that the lining stays intact over the tunnel and acts as its own protective cover. That is what lets us treat achalasia or a tumour under the lining without any incision on the abdomen. But it demands training and the right choice of patient, and I would rather decline than treat the wrong one.” Would you like to learn whether third space endoscopy is suitable for different GI conditions? Enquire Now Call now How Does Third Space Endoscopy Work? The “third space”: This is the potential space between the inner lining (mucosa) and the muscle layer of the gut wall. Fluid is injected to lift the lining and create room to work. Our service page on third space endoscopy covers the basics. A tunnel under the lining: A small opening is made in the lining, and the doctor tunnels beneath it to reach the muscle or the lesion. The lining above acts like a protective flap. Closing up: Once the work is done, the opening is closed with clips. Nothing is cut on the outside of the body. Built on ESD skills: The dissection technique is close to endoscopic submucosal dissection (ESD). If you want that background, read What Is Endoscopic Submucosal Dissection? Which Complex GI Conditions Can Third Space Endoscopy Treat? Achalasia (POEM): When the valve at the lower end of the food pipe won’t relax, food gets stuck. POEM cuts that muscle from inside. Trials suggest it works better than balloon stretching and about as well as surgery. See swallowing difficulty: causes and when it’s serious and balloon dilation for strictures. Severe gastroparesis (G-POEM): In stubborn cases, the muscle at the stomach’s exit (the pylorus) is cut so food can empty. It helps many patients, though long-term results are still being studied. Pouches in the food pipe (Z-POEM and D-POEM): The wall between a pouch (diverticulum) and the food pipe is divided so food stops collecting in it. Tumours under the lining (STER): Growths sitting beneath the surface can be removed through a tunnel, often without surgery. They’re usually assessed first with endoscopic ultrasound (EUS). See also endoscopic resection of tumors. What Determines the Right Treatment Approach? Your exact diagnosis: The right procedure depends on what’s wrong. Swallowing tests, endoscopy and sometimes a CT scan confirm the condition and rule out look-alikes before anything is planned. The lesion’s size, depth and position: For tumours, EUS shows which layer the growth sits in. That decides whether tunnelling is safe or whether another method suits better. Scarring from earlier treatment: Previous procedures or radiation can leave scar tissue in the wall. This can make tunnelling difficult, and it may change the plan. Your options and priorities: Balloon stretching, medicines and surgery are alternatives. Acid reflux can follow POEM, so it’s discussed beforehand. See our page on endoscopic treatment for GERD. Key Takeaways Third space endoscopy treatment works inside the gut wall through the mouth or anus, with no cuts on the skin. It treats achalasia, severe gastroparesis, diverticula and tumours beneath the lining. It’s an advanced technique that needs an experienced endoscopy team. Proper tests decide whether it suits you. Acid reflux can follow POEM. Ask about it before you decide. Frequently Asked Questions Is third space endoscopy a surgery? It’s an endoscopic procedure, not open or keyhole surgery. Everything is done through the scope, with no cuts on the skin. It’s still an advanced procedure and is done under anaesthesia. How long does recovery take? It varies with the procedure. Hospital stays are generally shorter than after surgery. Your team will give you a diet and activity plan. Our guide on recovery after endoscopic procedures gives a general idea. What are the risks? Bleeding, infection, a leak at the closure site and, after POEM, acid reflux. Your doctor will explain how these apply to your case. Do the results last? For achalasia, studies follow patients for up to five years and results are good. For gastroparesis, long-term outcomes are less certain. Follow-up visits are important. References A narrative review of update in POEM and endoscopic esophageal surgery, PMC Mastering the third space: innovations in intramural endoscopic surgery, World Journal of Gastrointestinal Endoscopy Disclaimer: This blog is for educational and informational purposes only and should not be considered professional advice.

Third Space Endoscopy: Treating Complex GI Conditions From Inside the Gut Wall Read More »

Banner illustrating heartburn: a woman clutching her chest with a highlighted flame and a circular inset of a stomach showing acid, about when to pursue care beyond antacids.

When Does Heartburn Need More Than Antacids?

The deciding factor is repetition. A bout after a heavy meal is ordinary, and an antacid is a reasonable answer to it. Heartburn that comes twice a week or more, wakes you at night or no longer settles with antacids may be GERD (gastroesophageal reflux disease), and it deserves a proper check. Trouble swallowing, weight loss, repeated vomiting, black stools or anaemia mean seeing a doctor soon, not reaching for another antacid. According to Dr. Vipulroy Rathod, Gastroenterology Specialist in Mumbai, “I always ask how many antacids a patient takes in a week. When the answer is more than two or three, the antacid has become the treatment for a condition nobody has examined. And heartburn that comes with trouble swallowing, weight loss or black stools should be looked at before it is treated.” Wondering whether your heartburn is ordinary acidity or something that needs a proper check? Enquire Now Call now When to See a Doctor for Heartburn? How often it happens: Heartburn twice a week or more, for several weeks, is the usual point where a doctor’s review makes sense. Antacids only neutralise acid for a short while. They don’t treat the reflux itself. Antacids stop being enough: If you need them daily, or the relief wears off sooner than it used to, the reflux is likely getting ahead of you. Our page on endoscopic treatment for GERD explains what options exist. Warning signs: Difficulty or pain while swallowing, unexplained weight loss, repeated vomiting, black stools, blood in vomit or anaemia need a check without delay. Read swallowing difficulty and when it’s serious, what GI bleeding looks like and esophageal cancer vs GERD. Chest pain: Burning in the chest can be your heart, not your stomach. If it comes with sweating, breathlessness, or pain spreading to the arm or jaw, go to an emergency room straight away. Doctors rule out the heart before blaming reflux. What Does Persistent Heartburn Treatment Involve? A planned course, not a random tablet: For typical heartburn without warning signs, doctors usually prescribe an acid-reducing tablet (a PPI) for about 8 weeks, taken 30 to 60 minutes before a meal. Long-term use should be reviewed by your doctor, not self-managed. Simple changes that help: Stopping smoking and raising the head of your bed can ease night-time reflux. Stress can make it worse too. See can stress make GERD worse? Endoscopy when it’s not settling: If symptoms don’t respond to treatment, a scope lets the doctor look at the food pipe directly. Our guide on questions to ask before an endoscopy helps you prepare. Options for stubborn reflux: When tablets aren’t enough, endoscopic procedures such as ARMA (Anti-Reflux Mucosal Ablation) may be considered after a proper work-up. What Determines the Right Treatment Approach? How often and how strong the symptoms are: Mild heartburn less than twice a week can often be managed with short-term measures. Frequent symptoms usually call for a proper treatment course. Whether warning signs are present: If you have trouble swallowing, weight loss, bleeding or anaemia, the first step is an endoscopy, not a trial of tablets. How you respond to the first course: If your symptoms don’t improve, or return as soon as the tablets stop, the next step is usually an endoscopy, sometimes followed by reflux testing. Your risk of complications: Reflux that has gone on for years, especially with other risk factors such as smoking or being male, raises the chance of Barrett’s oesophagus. Read what Barrett’s esophagus is and whether acid reflux can cause esophageal cancer. Key Takeaways Occasional heartburn is common and antacids are fine for it. Heartburn twice a week or more, or needing antacids every day, is a reason to see a doctor. Trouble swallowing, weight loss, vomiting, black stools or anaemia need prompt attention. Persistent heartburn treatment usually starts with a supervised course, with endoscopy if it doesn’t settle. Never ignore chest pain. Rule out the heart first. Frequently Asked Questions How often is too often to take antacids? If you need them more than twice a week for several weeks, it’s time to see a doctor. Regular use means the reflux itself needs treating. Can heartburn actually be a heart problem? Yes, the two can feel alike. Chest pain with sweating, breathlessness or pain in the arm or jaw is an emergency. Get it checked before assuming it’s acidity. Is it safe to take acid tablets for a long time? Many people use them safely, but long-term use should be reviewed regularly. Your doctor may lower the dose or change how you take them. Don’t stop or restart them on your own. Will I need an endoscopy for heartburn? Not everyone does. It’s usually advised if you have warning signs, if treatment hasn’t worked, or if you have several risk factors for complications. References ACG Clinical Guideline: Diagnosis and Management of Gastroesophageal Reflux Disease, PMC Updated ACG guidelines for GERD, Cleveland Clinic Journal of Medicine Diagnosis and Management of GERD: Patient Guideline Summary, Guideline Central GERD Primary Care Pathway Disclaimer: The information shared in this content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified gastroenterologist for guidance specific to your condition.

When Does Heartburn Need More Than Antacids? Read More »

How Is a Foreign Body Removed Endoscopically From the GI Tract

How Is a Foreign Body Removed Endoscopically From the GI Tract?

Most swallowed foreign bodies pass through the GI tract without intervention. Around 80% clear spontaneously. The other 20% get stuck at the cricopharyngeus, the lower oesophageal sphincter, the pylorus, or anywhere a prior stricture or surgical anastomosis creates a hold-up point. When that happens, the endoscope goes in. Not a scan, not a wait-and-watch the scope, the right accessory for the object, and extraction before erosion, perforation, or migration puts the object somewhere it can’t be reached. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Foreign body ingestion looks different depending on what was swallowed and where it’s sitting. A button battery anywhere is an emergency. A fish bone in the stomach in a well adult can wait till morning. The object and the location together decide the timeline not the symptom alone.” Swallowed object with chest pain, drooling, or inability to swallow? Enquire Now Call now Which Foreign Bodies Need Urgent Endoscopic Removal? Not every swallowed object goes straight to the scope. These specific situations don’t wait. Button batteries: Electrical current generates hydroxide necrosis within two hours — oesophageal perforation and tracheo-oesophageal fistula follow. Emergency removal, no exceptions, no delays. Sharp objects in the oesophagus: Fish bones, open safety pins, needles anything sharp sitting in the oesophagus comes out urgently. The same object past the pylorus in a well patient can usually be monitored. Complete food bolus impaction: Total oesophageal blockage with drooling and inability to swallow needs removal within hours. Prolonged impaction causes mucosal pressure necrosis. Multiple magnets: Two or more magnets swallowed separately attract through bowel wall layers silent fistula and perforation follow. Urgent endoscopy or surgery regardless of symptoms. Objects past the duodenum that aren’t sharp or battery-type usually pass serial X-rays confirm movement, and surgery only comes in when an object stalls in the same position for more than three days. What Accessories Does the Endoscopist Use? Object type decides the tool. No single accessory works for everything. Rat-tooth and alligator forceps: For flat, firm objects: coins, disc batteries, tablet fragments. Grip the object directly and withdraw alongside or through the scope. Polypectomy snare: For food boluses and larger irregular objects. Loop cinched around the object and withdrawn; handles things forceps can’t grip cleanly. Retrieval basket: Mesh opened around smooth round objects marbles, nuts, small balls and closed to capture. Forceps slip off these; the basket doesn’t. Overtube: Placed over the scope before insertion for sharp objects. An experienced endoscopist pulls the sharp object into or alongside the overtube on the way out, protecting the mucosa and airway from the object’s edges. After retrieval, the impaction site gets inspected for lacerations, ulceration, or perforation. Button battery sites in particular look deceptively minor at extraction and worsen significantly within hours. What Happens When Endoscopy Can’t Retrieve the Object? Endoscopy succeeds in over 95% of cases. The remaining situations have a defined path. Beyond endoscopic reach: Past the ligament of Treitz, standard upper endoscopy can’t access it. Colonoscopy reaches from below to the terminal ileum. Anything between the two needs enteroscopy, radiology, or surgery depending on urgency. Perforation at scope: Free air on fluoroscopy or a visible mucosal defect with extraluminal content; scope withdraws immediately and surgical referral follows. Embedded objects: Partially eroded through the wall or embedded in tissue, an object can’t be pulled free without completing the perforation. Surgery is the right call. Failed first attempt: A second attempt with a different accessory or patient position is reasonable. GI cancer treatment teams handle cases where an underlying stricture or malignancy drove the impaction and needs addressing separately. People who notice persistent difficulty swallowing or food coming back up after a foreign body episode should get a follow-up endoscopy mucosal injury and oesophageal stricture from the impaction can produce symptoms that outlast the original object by weeks. Key Takeaways 80% of swallowed foreign bodies pass spontaneously; the 20% that don’t need endoscopy, and the object plus location together decide urgency Button batteries are the only true GI foreign body emergency; hydroxide necrosis starts within two hours Multiple magnets anywhere need removal even without symptoms they attract silently through bowel loops Sharp objects in the oesophagus are urgent; the same object past the pylorus in a well patient can usually be monitored The overtube isn’t optional for sharp objects it protects the mucosa and airway on withdrawal Post-retrieval mucosal inspection matters; button battery necrosis looks minor at extraction and progresses hours later Frequently Asked Questions Do all swallowed foreign bodies need endoscopy? No, around 80% pass spontaneously. Sharp objects, button batteries, complete obstruction, and multiple magnets need removal. How urgent is a swallowed button battery? Emergency hydroxide necrosis begins within two hours and removal cannot wait for a scheduled list. Can colonoscopy remove objects from the colon? Yes, colonoscopy retrieves objects in the colon and terminal ileum when upper endoscopy can’t reach them. What if endoscopy fails to retrieve the object? A second attempt with a different tool is reasonable; perforation, embedment, or a second failure goes to surgery. References Upper Gastrointestinal Tract Foreign Bodies, Korean Journal of Helicobacter and Upper Gastrointestinal Research (PubMed) Endoscopic management of foreign bodies in the upper gastrointestinal tract: A review, World Journal of Gastrointestinal Endoscopy Disclaimer: This blog is for educational and informational purposes only and should not be considered professional advice.

How Is a Foreign Body Removed Endoscopically From the GI Tract? Read More »

How Is a Pancreatic Duct Stent Placed During ERCP

How Is a Pancreatic Duct Stent Placed During ERCP?

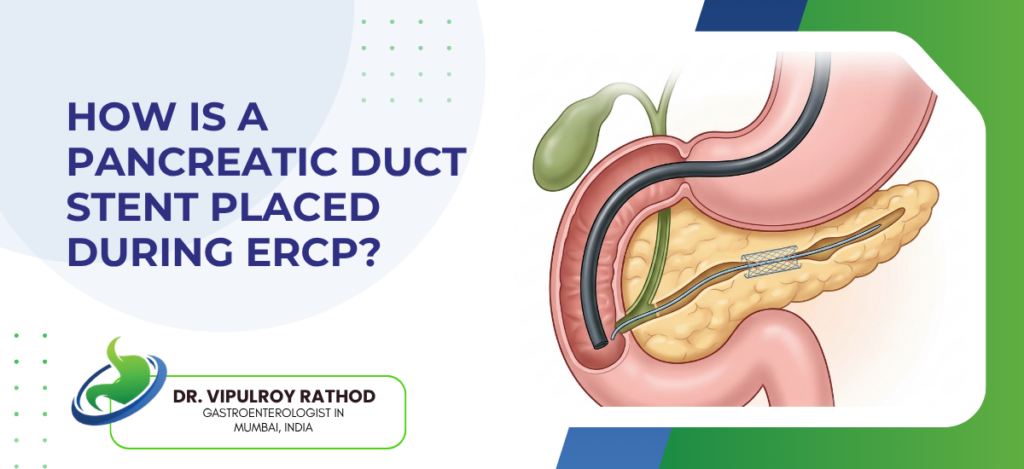
ERCP reaches the pancreatic duct through a side-viewing duodenoscope positioned at the papilla of Vater. A guidewire goes into the duct under fluoroscopy, contrast maps the duct anatomy, and the stent deploys over the wire. Sounds simple. Pancreatic duct cannulation is technically harder than biliary access; the duct is narrower, and placing the wrong stent in the wrong position changes both outcome and complication risk. Which stent, how far it goes, and whether it’s meant to stay or fall out all of that follows the indication, not a standard protocol. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Pancreatic stenting during ERCP isn’t one procedure; it’s several different decisions made in real time. Prophylactic stenting after a difficult cannulation is completely different from therapeutic stenting for a chronic stricture, and confusing the two is where complications start.” Upper abdominal pain with raised amylase or a dilated pancreatic duct on imaging? Enquire Now Call now Why Is a Pancreatic Duct Stent Placed During ERCP? The indication decides stent type, size, position, and whether removal is planned or spontaneous. Prophylaxis: Placed after difficult cannulation or sphincter of Oddi manometry to prevent post-ERCP pancreatitis; cuts risk in high-risk patients from around 13% to under 4%. Chronic stricture: A fibrous block in the main duct causes upstream dilatation and pain. A stent decompresses the duct and reduces pressure-related pain episodes over months. Duct leak: Disruption from surgery, necrosectomy, or trauma lets pancreatic juice escape. A stent bridging the disruption redirects flow and allows the leak to seal. Disconnected duct: Pancreatic necrosis can sever the upstream duct completely. EUS maps anatomy first ERCP stenting only works if continuity still exists. Pancreatitis treatment decisions at the ERCP table follow the pancreatogram a normal duct with a high-risk cannulation gets a prophylactic stent; a strictured or disrupted duct gets a therapeutic one, and the two look nothing alike technically. How Does the Stent Placement Procedure Work? The sequence from cannulation to deployment is defined; each step informs the next. Selective cannulation: Guidewire targets the pancreatic orifice specifically. Inadvertent biliary cannulation wastes time and increases papilla trauma. Pancreatogram: Contrast under fluoroscopy maps length, calibre, stricture location, and leak site. Stent choice follows from what the imaging shows not a pre-decided plan. Stent selection: Prophylactic stents are 3Fr to 5Fr, short, unflanged inside for spontaneous passage. Therapeutic stents are 7Fr to 10Fr, longer, flanged to hold position. Using a therapeutic stent where a prophylactic one was indicated causes duct injury. Deployment: Stent pushed over the wire, wire removed, position confirmed fluoroscopically. An experienced endoscopist verifies the proximal end sits across the target and the distal end clears into the duodenum. Post-procedure amylase at four hours a rise beyond three times normal defines post-ERCP pancreatitis regardless of whether a stent was placed. What Happens After the Stent Is in Place? What follows depends entirely on which indication drove the placement. Prophylactic stents: Fall out spontaneously within days. X-ray at two weeks confirms passage; retention past three to four weeks causes ductal changes the stent was placed to prevent. Therapeutic exchanges: Plastic stents for chronic strictures block within three to six months. Planned exchange at that interval, escalating to multiple simultaneous stents, progressively dilates the stricture over one to two years. Leak stents: Stay until imaging confirms duct wall healing typically four to eight weeks, confirmed by repeat pancreatogram or cross-sectional imaging. When stenting fails: A stricture not responding after twelve months of serial plastic stenting needs a covered metal stent or surgical referral not more plastic stent exchanges. People with known pancreatic disease who notice signs of pancreatic enzyme deficiency alongside their ERCP history should raise both together; stent-related duct changes and exocrine insufficiency can develop in parallel. Key Takeaways Prophylactic and therapeutic pancreatic stents are different devices for different problems; the wrong stent in a normal duct causes injury Post-ERCP pancreatitis risk drops from around 13% to under 4% with a correctly placed prophylactic stent in high-risk cases The pancreatogram taken during ERCP is the decision point; stent choice follows the imaging, not the pre-procedure plan Prophylactic stents should fall out within days; retained stents past three to four weeks cause the damage they were placed to prevent Therapeutic stents for strictures need exchange every three to six months they block predictably and aren’t permanent Twelve months of serial stenting without stricture response means a different approach, not more of the same Frequently Asked Questions Is pancreatic duct stenting painful? ERCP is performed under sedation; post-procedure abdominal discomfort for 24 to 48 hours is common, but the procedure itself isn’t felt. How long does a pancreatic stent stay in place? Prophylactic stents pass within days; therapeutic stents for strictures are exchanged every three to six months. Can a pancreatic stent cause complications? Yes, stent migration, duct injury from prolonged retention, and post-ERCP pancreatitis are the main risks. When is surgery preferred over ERCP stenting? When twelve months of serial plastic stenting produces no meaningful stricture improvement, surgical drainage is considered. References Randomized controlled trial of pancreatic stenting to prevent pancreatitis after endoscopic retrograde cholangiopancreatography, World Journal of Gastroenterology Clinical usefulness and current problems of pancreatic duct stenting for preventing post-ERCP pancreatitis, World Journal of Clinical Cases Disclaimer: The information shared in this content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified gastroenterologist for guidance specific to your condition.

How Is a Pancreatic Duct Stent Placed During ERCP? Read More »

How Is Celiac Disease Diagnosed

How Is Celiac Disease Diagnosed?

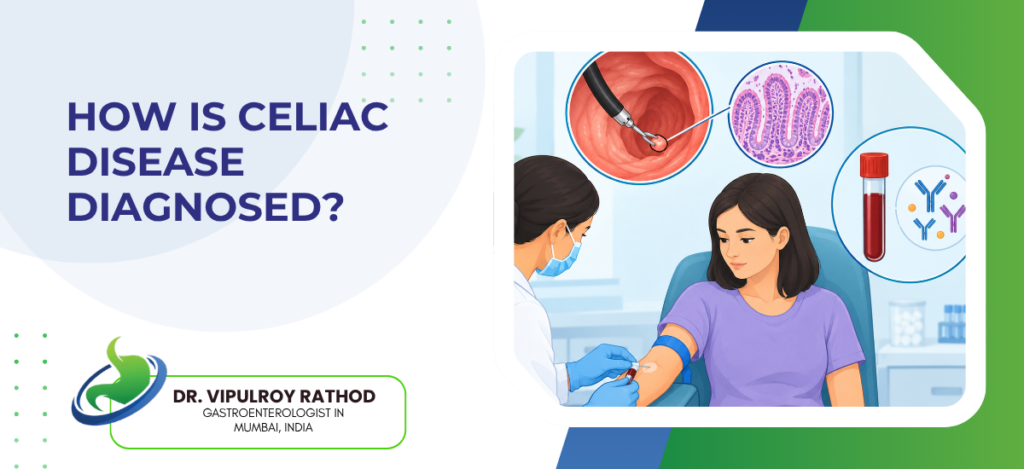
Two steps lead to the diagnosis. The first is a blood test, chiefly tissue transglutaminase IgA (tTG-IgA), along with a total IgA level to check for deficiency. If it is positive, most adults need an upper endoscopy with small-bowel biopsies to settle the matter. The rule that matters most is to carry on eating gluten until every test is done, since cutting it out early can hide genuine disease. According to Dr. Vipulroy Rathod, Gastroenterology Specialist in Mumbai, “Almost everyone who suspects celiac disease wants to start the diet that same day. Both tests depend on gluten being in the body. When it is removed, the antibodies fall and the lining of the small bowel begins to heal, so a genuine case can look normal. Test first, and change the diet afterwards.” Which tests help confirm celiac disease? Enquire Now Call now What Tests Are Used for Celiac Disease Diagnosis? tTG-IgA blood test: This is the first test almost everyone gets. It picks up antibodies your body makes when gluten damages the gut lining, and it works best while you’re still eating gluten. Total IgA level: It’s ordered alongside tTG-IgA. A small number of people with celiac disease (around 3 in 100) are IgA deficient and can test falsely negative. In that case, IgG-based tests such as tTG-IgG or DGP are used instead. Upper GI endoscopy with duodenal biopsy: This is the confirming test in most adults. A thin scope goes through the mouth, and small samples are taken from the first part of the small intestine. See our overview of endoscopic services, and read what to ask before an endoscopy. HLA-DQ2/DQ8 gene test: This doesn’t diagnose celiac disease. A negative result, though, rules it out, so it’s useful when someone has already gone gluten-free or when results don’t add up. What Happens During the Endoscopy and Biopsy? The procedure: You’re sedated, and the scope passes through your mouth into the duodenum. It’s a short procedure, and the doctor also checks your food pipe and stomach on the way. Why several samples: Celiac damage can be patchy, so guidelines recommend taking four or more biopsies. The pathologist then looks for flattened villi (the tiny finger-like folds that absorb food) and extra inflammatory cells. Afterwards: Most people go home the same day. Our guide to recovery after endoscopic procedures covers what to expect. If the scope isn’t enough: When symptoms continue or the picture is unclear, the small bowel may need a closer look. See capsule endoscopy and double balloon endoscopy. What Determines the Right Diagnostic Approach? Whether you’re eating gluten now: Tests only work if gluten is in your diet. UK guidance suggests including it in more than one meal a day for at least six weeks before testing. Chapati, bread and biscuits all count. Your age: Adults usually need a biopsy. Some children with very high tTG-IgA levels and a second positive antibody test can be diagnosed without one, but only under a specialist’s guidance. Your antibody results: A high tTG-IgA gives a stronger case. A negative result with a normal total IgA makes celiac disease less likely, but not impossible if your symptoms strongly point to it. Your symptoms and history: Long-standing bloating, diarrhoea, weight loss or anaemia, or a close relative with celiac disease, all raise suspicion. Similar symptoms can come from other conditions, so see bloating after every meal and microscopic colitis. Key Takeaways Celiac disease diagnosis starts with a tTG-IgA blood test plus a total IgA level. In most adults, an endoscopy with duodenal biopsies confirms it. Don’t stop eating gluten before testing is finished. A negative blood test doesn’t always close the case if your symptoms are strong. If you’re already gluten-free, a gluten challenge or a gene test may be needed. Frequently Asked Questions Can celiac disease be diagnosed with a blood test alone?  In adults, usually not. A positive blood test is normally confirmed with an endoscopy and biopsy. In some children with very high antibody levels, the biopsy can be skipped. Should I stop eating gluten before the tests? No. Stopping early can give false-negative results on both the blood test and the biopsy. Keep eating gluten normally until your doctor says the testing is complete. What if I’m already on a gluten-free diet? Speak to your gastroenterologist. You may be asked to eat gluten again for a few weeks before repeat testing, or to have an HLA gene test, which isn’t affected by diet. Does a negative blood test rule out celiac disease? Not always. IgA deficiency or a low antibody level can hide it. If your symptoms still point to celiac disease, an endoscopy with biopsies may be advised. References Diagnosis and Management of Celiac Disease: ACG Guidelines, American Family Physician AGA Clinical Practice Update on Diagnosis and Monitoring of Celiac Disease, PubMed Disclaimer: This blog is for educational and informational purposes only and should not be considered professional advice.

How Is Celiac Disease Diagnosed? Read More »

How Is Small Intestinal Bacterial Overgrowth (SIBO) Diagnosed?

How Is Small Intestinal Bacterial Overgrowth (SIBO) Diagnosed?

Bacteria belong in the colon. When they overgrow in the small intestine, they start fermenting carbohydrates before the body can absorb them. Gas accumulates. Bloating follows. Over time, genuine malnutrition sets in because nutrients are being consumed by bacteria before they reach the bloodstream. SIBO gets missed routinely not because it’s rare, but because it looks like IBS on the outside and nobody orders the test that would catch it. And treating IBS when SIBO is the actual driver produces results that look exactly like IBS treatment failure.   According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “SIBO gets missed because bloating and altered bowel habits get labelled IBS without a breath test. When IBS treatment fails repeatedly, SIBO should be on the list a hydrogen breath test tells you something a colonoscopy can’t.” Bloating and loose stools that haven’t responded to standard IBS treatment? Enquire Now Call now What Tests Are Used to Diagnose SIBO? Breath tests are non-invasive and practical. But each one has limits, and the gas type changes what the result means. Glucose breath test: Glucose is absorbed in the upper small bowel bacteria fermenting it before that happens produces a hydrogen or methane rise within 90 minutes. Reliable for proximal SIBO specifically. Lactulose breath test: Lactulose travels the full small bowel length unabsorbed. A double-peak pattern suggests SIBO, but interpretation is genuinely harder than glucose testing and false positives are more common. Jejunal aspirate: Small bowel fluid sampled directly via endoscopy and cultured. Over 10³ colony-forming units per mL confirms overgrowth the technical gold standard, used when breath tests come back equivocal. Gas type identification: Hydrogen links to diarrhoea-predominant symptoms. Methane, now called intestinal methanogen overgrowth, drives constipation. Hydrogen sulphide needs a separate panel. An experienced endoscopist decides which test matches the symptom pattern before ordering anything. IBS treatment that keeps failing despite dietary compliance is the clinical signal — SIBO drives a meaningful chunk of IBS-D cases and doesn’t respond to gut-directed IBS therapy at all. What Conditions Create the Environment for SIBO? SIBO doesn’t appear from nowhere. Finding what opened the door to it changes whether it comes back. Motility disorders: Slow small bowel transit lets bacteria pool where they shouldn’t. Diabetic gastroparesis, scleroderma, and post-surgical dysmotility are the usual culprits treat the motility problem or SIBO keeps returning. Low stomach acid: Long-term PPI use, autoimmune gastritis, prior gastric surgery all reduce the acid barrier that limits bacterial passage into the small bowel. Worth reviewing medication history before antibiotic treatment starts. Structural problems: Strictures, adhesions, small bowel diverticula, and stagnant loops let bacteria accumulate. Colonoscopy and small bowel imaging map structural causes that no breath test can show. Post-infectious trigger: A gastroenteritis episode damages the interstitial cells of Cajal that drive the migrating motor complex the gut’s housekeeping mechanism. Without it, bacteria that should be cleared downstream aren’t. People who alternate between constipation and diarrhoea without a clear trigger and haven’t responded to standard management need a predisposing cause worked up alongside the breath test the cause, not just the bacteria. How Is SIBO Treated Once the Diagnosis Is Confirmed? Treatment follows the gas type. Not symptoms. Not a default antibiotic protocol. Rifaximin: Non-absorbed antibiotic, stays in the gut lumen. First-line for hydrogen-dominant SIBO. Two-week course response confirmed on a repeat breath test, not assumed from how the patient feels. Rifaximin plus neomycin: Methane-dominant IMO needs both agents. Neomycin targets methanogens that rifaximin alone doesn’t clear the combination outperforms monotherapy in constipation-predominant cases. Elemental diet: Liquid formula absorbed proximally, nothing left distally to ferment. Reduces bacterial load effectively used when antibiotics have failed or aren’t tolerated. Two weeks is a significant commitment. Fixing the underlying cause: Stopping unnecessary PPIs, adding prokinetics post-treatment, correcting structural issues where possible. Skip this step and SIBO recurrence within three to six months isn’t unusual. Understanding how SIBO overlaps with IBD and IBS diagnostically matters: all three produce bloating and altered bowel habits, and getting the diagnosis wrong means the right drug is treating the wrong condition. Key Takeaways SIBO looks like IBS on symptoms only a breath test separates them, not a clinical impression Which gas the test identifies determines which antibiotic gets used; guessing the drug without knowing the gas type is the main reason SIBO treatment fails Jejunal aspirate culture is the gold standard but reserved for cases where breath tests don’t give a clear answer Finding the predisposing cause motility disorder, low acid, structural issue is what stops SIBO from coming back Repeat breath test confirms treatment response; feeling better doesn’t Recurrence is the default outcome when the underlying driver isn’t corrected alongside antibiotics Frequently Asked Questions Is a breath test enough to confirm SIBO? It’s the practical first-line test; jejunal aspirate culture is more definitive but reserved for equivocal results. What’s the difference between hydrogen and methane SIBO? Hydrogen produces diarrhoea and responds to rifaximin; methane causes constipation and needs an added antibiotic. Can SIBO come back after treatment? Yes, recurrence is common when the predisposing cause isn’t addressed alongside the antibiotic course. How long does SIBO treatment take? Rifaximin runs for two weeks; response should be confirmed with a repeat breath test, not assumed from symptoms. References Small Intestinal Bacterial Overgrowth NIH/NCBI StatPearls SIBO Diagnosis and Treatment American College of Gastroenterology Disclaimer: The information shared in this content is for educational purposes only and is not a substitute for professional medical advice, diagnosis or treatment. Please consult a qualified gastroenterologist for guidance specific to your condition.

How Is Small Intestinal Bacterial Overgrowth (SIBO) Diagnosed? Read More »

How Are Esophageal Varices Treated Endoscopically

How Are Esophageal Varices Treated Endoscopically?

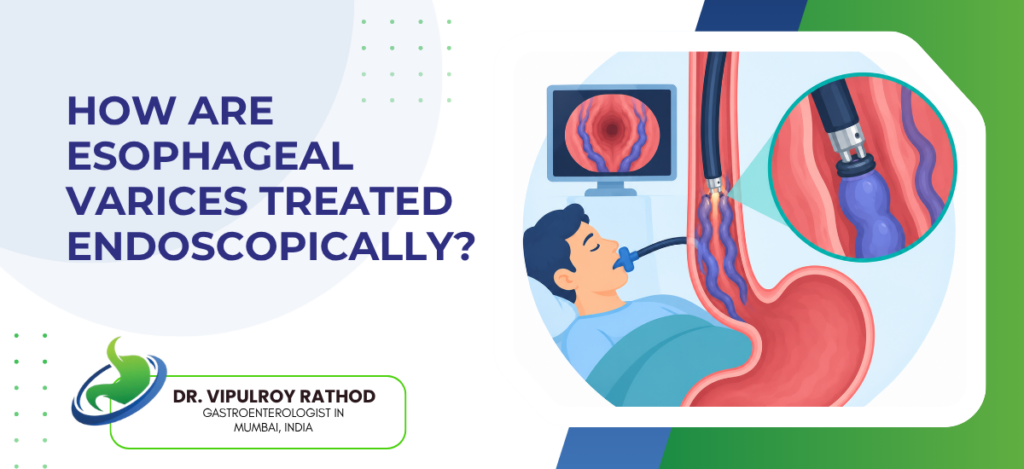
When the liver scars, blood can’t flow through it normally. Portal pressure climbs. Blood reroutes through smaller vessels, including the veins lining the lower oesophagus, which aren’t designed for that volume or pressure. More than half of all cirrhosis patients develop varices. First bleed mortality sits between 15 and 20%. The endoscope is the primary tool for stopping active bleeding, for preventing the first bleed, and for monitoring between sessions. No medication does what band ligation does. And the window for intervention is narrow. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Variceal bleeding is one of the few genuine GI emergencies where minutes change outcomes. Band ligation within 12 hours of presentation is the standard; waiting for the patient to stabilise without scoping first is the wrong sequence.” Known cirrhosis with vomiting blood or black stools? Enquire Now Call now What Endoscopic Techniques Treat Esophageal Varices? The technique depends on where the varix sits, how actively it’s bleeding, and what the scope can access. Band ligation: Rubber bands at the varix base cut off blood supply and cause thrombosis. First-line for acute bleeding and elective obliteration. Sclerotherapy: Sclerosant injected into or beside the varix when banding isn’t technically possible or the view is too poor for bands. Glue injection: Cyanoacrylate for gastric varices polymerises on blood contact and occludes the vessel. EVL doesn’t work reliably in the stomach fundus. Drug-scope combination: Vasoactive drugs go in before the scope to narrow portal vessels and clear the field. An experienced endoscopist runs both arms together. Liver cirrhosis stage directly determines how fast varices grow treating the liver disease and the varices as separate programmes is where management goes wrong. How Do Prophylaxis Stages Work in Variceal Management? Varices don’t always bleed on first presentation. What happens next depends entirely on what the screening scope finds. Screening scope: Every new cirrhosis diagnosis gets an upper GI scope varix grade, red wale signs, and location together set the management path. Primary prophylaxis: Large varices or red wale signs in someone who hasn’t bled yet get treated with EVL or beta-blockers. Watching confirmed high-risk varices isn’t a valid option. Acute bleeding: Vasoactive drugs before the scope, EVL within 12 hours, antibiotic cover throughout. Antibiotics cut rebleeding risk in cirrhotics by half. Secondary prophylaxis: First bleed means 60% rebleeding risk within a year without treatment. EVL every two to four weeks until obliteration is confirmed on scope not assumed from symptoms. EUS shows perforating vessels and collateral anatomy the standard scope misses, useful specifically in recurrent or refractory cases where routine banding keeps failing. When Does Endoscopic Treatment Stop Being Enough? EVL handles most bleeds. Some it doesn’t. The escalation path is defined. TIPS: Two failed haemostasis attempts mean TIPS, a portosystemic shunt that drops portal pressure when the scope has reached its limit. Balloon tamponade: Sengstaken-Blakemore tube as a mechanical bridge. 24 hours maximum. Buys time for TIPS, not a standalone treatment. Post-obliteration follow-up: Varices come back as portal hypertension continues. Scope at three to six months post-obliteration, then annually indefinitely. Liver disease itself: Fatty liver progressing to NASH cirrhosis drives variceal recurrence. Repeated banding without treating the underlying disease is managing a symptom on a loop. People with known liver disease noticing raised liver enzymes on routine blood tests alongside new upper abdominal fullness or easy bruising need a variceal screening scope portal hypertension builds silently before the first bleed announces it. Key Takeaways First bleed mortality from varices is 15 to 20% that number moves with how fast the scope gets in EVL is first-line; sclerotherapy comes in when banding isn’t technically possible High-risk varices on screening scope mean treatment starts not a monitoring plan One bleed without secondary prophylaxis means 60% chance of another within a year Symptom improvement after EVL doesn’t mean obliteration only a follow-up scope confirms it Varices come back as cirrhosis worsens; the endoscopic programme doesn’t end at obliteration Frequently Asked Questions What is the first-line endoscopic treatment for esophageal varices? Endoscopic variceal ligation rubber band application for both acute bleeding and elective obliteration. How many EVL sessions does variceal obliteration take? Three to five sessions typically, every two to four weeks, confirmed on scope rather than assumed. Can esophageal varices return after treatment? Yes, portal hypertension doesn’t resolve with obliteration, so varices regrow and surveillance continues. When is TIPS used instead of endoscopy? Two failed haemostasis attempts on scope; that’s when TIPS decompresses portal pressure instead. References Endoscopic Treatment of Esophageal Varices in Liver Cirrhosis World Journal of Gastroenterology Endoscopic Treatment and Prevention of Acute Variceal Hemorrhage Disclaimer: This blog is for educational and informational purposes only and should not be considered professional advice.

How Are Esophageal Varices Treated Endoscopically? Read More »

When Does a Gastric Ulcer Require Endoscopic Intervention

When Does a Gastric Ulcer Require Endoscopic Intervention?

Gastric ulcers heal with medication. H. pylori eradication, stopping NSAIDs, acid suppression are the standard path, and it works for the majority. But some ulcers don’t behave that way. They bleed. They perforate. They don’t heal on repeat endoscopy. Or they sit in a location and carry features that make a gastroenterologist suspicious of something worse than a benign ulcer. Those cases don’t wait for a medication trial. The scope goes in first sometimes the same night. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “A bleeding gastric ulcer with a visible vessel at the base isn’t a medication decision it’s an endoscopic emergency. The mortality difference between early endoscopic haemostasis and delayed intervention is well established and the window is narrow.” Stomach pain with vomiting blood or black stools recently? Enquire Now Call now Which Ulcer Features Make Endoscopic Intervention Necessary? A gastric ulcer found on a scan or raised by symptoms doesn’t automatically mean a scope that day. These specific features do. Active bleeding or haematemesis: Blood in vomit or black tarry stools from a gastric ulcer is an endoscopic emergency. The source gets identified, the bleeding vessel gets treated injection, thermal coagulation, haemostatic clip and the decision about whether the patient needs surgery is made based on what the scope finds, not based on waiting for the next blood count. Visible vessel or clot at the ulcer base: Even without active bleeding at the time of scoping, a non-bleeding visible vessel or an adherent clot at the ulcer crater carries a high rebleeding risk within 72 hours. That finding changes management: endoscopic treatment happens at the same scope rather than sending the patient home on a PPI. Ulcer not healing at follow-up scope: Benign gastric ulcers should show measurable healing at 6 to 8 weeks on medication. One that hasn’t reduced in size or has grown needs repeat biopsies and possible endoscopic resection. A gastric ulcer that doesn’t heal on adequate therapy is malignant until proven otherwise. Suspicious ulcer morphology: Irregular raised edges, a nodular base, surrounding mucosal convergence, or an ulcer sitting in the greater curvature these are endoscopic features that prompt multiple biopsies across the ulcer margin and base at the first scope, not a trial of medication and a recheck. Endoscopic treatment for upper GI conditions has replaced surgery as the first intervention for most bleeding ulcers — with rebleeding rates after successful endoscopic haemostasis well under 20% in experienced hands versus the significantly higher morbidity of emergency ulcer surgery. What Happens During Endoscopic Treatment of a Gastric Ulcer? The scope does several things at once: diagnoses, stages, and treats in a single session. Forrest classification on arrival: The endoscopist grades the ulcer immediately active spurting, oozing, visible vessel, adherent clot, clean base and that classification drives what happens next in real time. Forrest Ia and Ib bleed and get treated on the table. Forrest IIa and IIb get treated preventively. IIc and III get biopsied and managed medically. Injection therapy: Dilute adrenaline injected into the four quadrants around the bleeding point compresses the vessel and buys time. Used as a first step before definitive haemostasis not as a standalone treatment, because rebleeding rates with injection alone are unacceptably high. Thermal and mechanical haemostasis: Heater probe, argon plasma coagulation, haemostatic clips applied after injection to the vessel itself. Clips are particularly useful for ulcers with a clearly visible vessel, as an experienced endoscopist can deploy them precisely without thermal injury to surrounding tissue. Biopsies regardless of appearance: Every gastric ulcer gets biopsied at endoscopy minimum six samples from the margin and base. Benign-looking ulcers have turned out to be early gastric cancers on histology. The appearance doesn’t override the biopsy. Ever. People who’ve noticed persistent upper abdominal pain alongside symptoms like food regurgitation or difficulty swallowing should mention both together because that combination shifts the upper GI differential considerably beyond a simple ulcer. What Comes After Endoscopic Intervention? The scope treated the immediate problem. What follows determines whether it stays treated. High-dose PPI infusion post-haemostasis: After successful endoscopic bleeding control, IV pantoprazole runs for 72 hours, the period when rebleeding risk is highest. Oral high-dose PPI continues after that. Stopping early because the patient feels better is the most common reason for rebleeding readmission. H. pylori eradication as non-negotiable: If H. pylori is found and it’s present in the majority of non-NSAID gastric ulcers, eradication is confirmed with a breath test or stool antigen test 4 weeks after completing treatment. Not assumed. Confirmed. Reinfection and failed eradication both drive recurrence. Follow-up scope at 6 to 8 weeks: Every gastric ulcer needs a repeat endoscopy to confirm healing and re-biopsy if healing is incomplete or the appearance has changed. This isn’t optional: follow-up for gastric ulcers is the one upper GI condition where a follow-up scope is mandatory because of malignancy risk, regardless of how the patient feels. Surgical referral for endoscopic failures: Rebleeding after two endoscopic attempts, perforation, or a bleeding ulcer in a location technically inaccessible to haemostasis GI cancer treatment pathways and surgical referral run alongside endoscopy in those situations, not after multiple failed attempts have already cost time. Understanding what persistent upper GI symptoms like burping and acid return actually signal is often where gastric ulcer cases start symptoms that seem minor for months before a scope finds the ulcer that’s been sitting there. Key Takeaways Most gastric ulcers heal with medication the ones that don’t, or that present with bleeding, need endoscopy first and medication second A visible vessel at the ulcer base during scoping triggers endoscopic treatment even without active bleeding; rebleeding risk within 72 hours is too high to observe Every gastric ulcer gets biopsied regardless of how benign it looks appearance doesn’t override histology A gastric ulcer not healing at 6 to 8 weeks on adequate therapy is malignant until the biopsy proves otherwise H. pylori eradication needs confirming with a test, not assuming from treatment completion — failed eradication is a common driver of recurrence

When Does a Gastric Ulcer Require Endoscopic Intervention? Read More »

How Do Doctors Differentiate IBS From IBD?

How Do Doctors Differentiate IBS From IBD?

Three shared letters. A handful of shared symptoms. After that, almost nothing in common. IBS is a functional gut disorder: the bowel misbehaves, but the wall itself is structurally intact. IBD means actual tissue damage: ulceration, inflammation, bleeding Crohn’s disease or ulcerative colitis eating through the bowel wall. The treatment gap between them is not small. One gets dietary therapy and motility management. The other gets immunosuppressants, biologics, and sometimes a surgeon. Diagnosing the wrong one isn’t just a delay it’s the wrong treatment running for months or years. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “IBS and IBD overlap on symptoms enough that patients spend months, sometimes years, on IBS treatment before IBD gets picked up. Blood, weight loss, night symptoms those are the flags that should have triggered a scope much earlier.” Bowel symptoms that haven’t been properly investigated yet? Enquire Now Call now What Symptoms Overlap and What Sets Them Apart? On the surface, both conditions produce cramping, urgency, and altered bowel habits. But a few specific details change the picture entirely. Blood in stool: IBS doesn’t produce rectal bleeding. Not occasionally. Not mildly. Blood in stool alongside bowel symptoms belongs to IBD until a scope proves otherwise and that finding alone should end the IBS conversation and start the investigation. Night-time symptoms: When someone’s woken from sleep by diarrhoea or cramping repeatedly, that’s not a functional condition. IBS settles when the nervous system settles. Something structural or inflammatory driving symptoms at 2am means the gut isn’t responding to sleep. IBD behaves that way; IBS doesn’t. Fever and weight loss: Neither fits IBS. Crohn’s and ulcerative colitis generate systemic inflammation raised temperature, dropping weight, a level of fatigue that goes well beyond what altered bowel habits alone explain. IBS makes people uncomfortable. IBD makes people unwell. Trigger pattern: IBS symptoms track food and stress fairly reliably and usually improve after passing stool. IBD doesn’t behave that predictably urgency that doesn’t resolve after opening the bowel, symptoms that don’t follow a clear dietary pattern, flares that come without an obvious trigger. Rectal bleeding with bowel urgency starting from the rectum upward is characteristic of ulcerative colitis and anyone carrying an IBS label who develops that combination needs re-evaluation, not dietary advice. Which Investigations Actually Separate the Two? IBS gets diagnosed when everything comes back normal. IBD shows up on tests. Stool calprotectin: White blood cells flood an inflamed gut wall and calprotectin shows up in the stool. Normal in IBS, raised in IBD. Not a standalone diagnosis — but a raised result in someone labelled IBS is a direct trigger for scoping, not a reason to continue the FODMAP diet and recheck in three months. CRP and full blood count: Active gut inflammation raises CRP; chronic bleeding or malabsorption drops haemoglobin over time. Normal results in someone with a classic stress-linked bowel pattern are genuinely reassuring. Abnormal ones in someone “with IBS” aren’t. Colonoscopy with biopsies: This is where the question gets answered definitively. Colonoscopy shows the bowel wall ulcers, friability, skip lesions in Crohn’s, continuous rectal-upward inflammation in ulcerative colitis. IBS bowel wall is visually normal. And biopsies from mucosa that looks fine can still catch microscopic colitis, which produces diarrhoea with no visible changes at all. Small bowel imaging: Crohn’s reaches anywhere from mouth to anus including long stretches the colonoscope never sees. MRI enterography or capsule endoscopy covers the small bowel when Crohn’s is suspected but the colon looks clean. Skipping that step misses a meaningful proportion of cases entirely. Crohn’s disease confined to the small bowel can produce months of pain and diarrhoea with no blood, a normal colonoscopy, and occasionally a normal calprotectin — looking indistinguishable from IBS until someone orders the right imaging. How Does Management Differ Once the Diagnosis Is Clear? Same symptoms going in. Completely different plans coming out. IBS: Low-FODMAP diet, gut-directed therapy, motility medication where needed. No immunosuppression. No biologics. The bowel wall isn’t damaged — treatment is about retraining how the gut responds, not suppressing inflammation that isn’t there. IBD induction: Active Crohn’s or ulcerative colitis flare gets treated to bring inflammation down first steroids, mesalazine, biologics depending on severity and location. Symptom management before inflammation control is the wrong sequence. IBD maintenance: Remission in IBD isn’t the same as cure. Stopping maintenance therapy because symptoms settle is a well-documented mistake relapse rates are high, and an experienced endoscopist checking mucosal healing matters because symptom control and bowel wall recovery don’t always happen together. Surgical trajectory: IBS carries essentially no surgical risk across a lifetime. Around 30% of Crohn’s patients will need surgery at some point: bowel resection, strictureplasty, drainage. Early accurate diagnosis in IBD directly affects whether the patient reaches that point or doesn’t. People managing a bowel pattern that alternates unpredictably without a clear food or stress trigger should ask their doctor about calprotectin testing before assuming IBS — because the test is simple and the stakes of missing IBD aren’t. Key Takeaways IBS and IBD aren’t variations of each other one has a structurally normal bowel wall, the other has visible damage, and that difference determines everything about treatment Blood in stool ends the IBS discussion immediately it always needs a scope, never reassurance Stool calprotectin is the most accessible first separator and doesn’t require a procedure — raised result means investigate, not recheck Crohn’s in the small bowel mimics IBS convincingly with a normal colonoscopy small bowel imaging is the test that catches it Feeling better in IBD isn’t the same as the bowel wall healing maintenance therapy exists for exactly that reason Getting the diagnosis right early in IBD cuts the lifetime surgical risk it’s not just about picking the right medication Frequently Asked Questions Can IBS turn into IBD over time? IBS doesn’t convert into IBD, but IBS-D patients carry a measurably higher long-term risk of developing IBD. Is calprotectin testing enough to confirm IBD? No, it flags gut inflammation and triggers investigation, but colonoscopy is what confirms the

How Do Doctors Differentiate IBS From IBD? Read More »

Scroll to Top
Call Now Button Seraphinite AcceleratorOptimized by Seraphinite Accelerator
Turns on site high speed to be attractive for people and search engines.