Dr. Vipulroy Rathod

Blog

Your blog category

Balloon Dilation for Strictures: What to Expect?

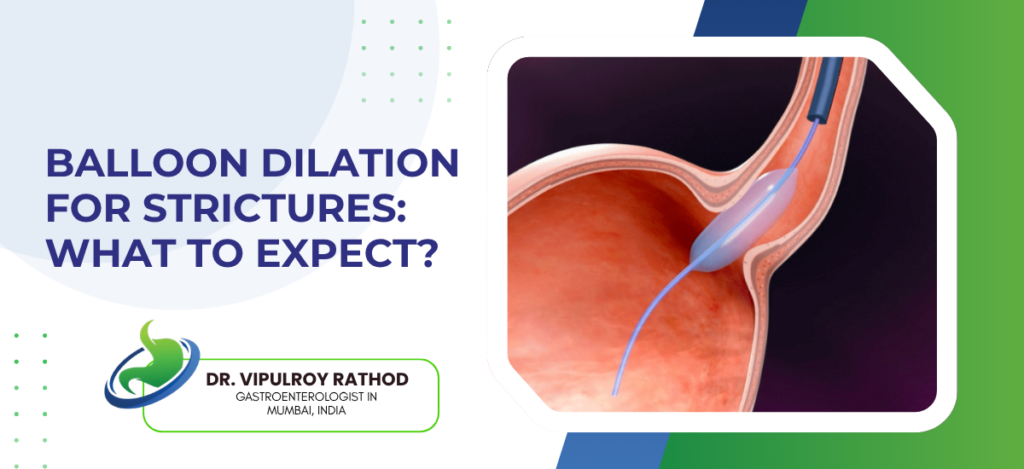
Balloon dilation widens a narrowed segment of the GI tract by inflating a balloon across the stricture through an endoscope, restoring normal passage without any incision. It’s used in the oesophagus, the small bowel, and the colon depending on where the narrowing sits, and in most cases the patient goes home the same day. What the procedure feels like, how many sessions it takes, and how durable the result is all depend on what caused the stricture in the first place. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Balloon dilation is one of those procedures that patients worry about far more than they need to. Done under sedation, it’s usually over in a few minutes and the improvement in swallowing or bowel passage is often immediate. The real clinical question isn’t the procedure itself but how often it needs repeating and whether the underlying cause is being addressed at the same time.” What Conditions Does Balloon Dilation Treat? The technique applies across several GI sites, with the balloon adapted in size to the stricture and the organ being treated. Peptic oesophageal strictures from years of acid reflux scarring the lower oesophageal lining are among the most common indications, and patients who’ve been managing progressive swallowing difficulty often notice improvement within days of the first dilation. In Crohn’s disease, short fibrotic strictures of the small bowel or colon that are causing obstructive symptoms respond well, and the procedure delays or avoids the bowel resection that would otherwise be the only alternative. After bowel or oesophageal surgery, anastomotic strictures at the joint site are a common complication and often need one or more dilation sessions before the narrowing stabilises and swallowing or passage returns to normal. Achalasia-related narrowing at the lower oesophageal sphincter can be opened with balloon dilation, though larger balloons and a slightly different technique apply here compared to a standard peptic stricture. Deciding which stricture needs dilation, how large the balloon should be, and whether the underlying condition needs addressing alongside it is where a specialist in IBD management shapes the whole approach. What Happens During and After the Procedure? Patients often arrive expecting something more uncomfortable than it turns out to be. Under sedation, the endoscope goes in first to visualise the stricture directly, and the balloon catheter is then passed through the scope and positioned across the narrowed segment. Inflating the balloon gradually opens the stricture by stretching it outward, held at target pressure for around a minute before deflation, with the degree of opening assessed through the scope immediately after. Most patients go home within a few hours, feeling mild discomfort or throat soreness after an oesophageal dilation that settles the same day, with diet restricted to liquids for 24 hours as a precaution. Follow-up depends on the cause. Some strictures hold well after one session; Crohn’s-related narrowings and refractory oesophageal strictures often need repeat dilation at planned intervals to maintain the result. Strictures from acid reflux are one of the clearest signs that GERD has gone beyond what medication alone can manage. Read more on GERD and endoscopy to understand when reflux complications like strictures need a scope rather than a prescription change. Why Choose Dr. Vipulroy Rathod for Balloon Dilation? Dr. Vipulroy Rathod has been performing balloon dilation for oesophageal, intestinal, and anastomotic strictures at Fortis Hospital Mulund for over 30 years, across the full range of causes including Crohn’s, peptic disease, post-surgical narrowing, and achalasia. That breadth means the balloon size, technique, and follow-up interval all get matched to the specific stricture rather than applied by rote. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for GI stricture assessment and balloon dilation. Book Appointment Call now Frequently Asked Questions What is balloon dilation for strictures? Balloon dilation widens a narrowed GI segment by inflating a balloon across it through an endoscope, restoring normal passage without surgery. What conditions require balloon dilation? It treats oesophageal strictures from reflux or surgery, Crohn’s intestinal strictures, anastomotic narrowing after bowel operations, and achalasia. How many sessions of balloon dilation are needed? Some patients need one session; others with Crohn’s or refractory strictures need repeat dilations at planned intervals over time. Is balloon dilation painful? Done under sedation, so no pain during the procedure. Mild throat discomfort after oesophageal dilation typically settles within a day. Reference Endoscopic Balloon Dilation for Crohn’s Disease-Associated Strictures — Korean Society of Gastrointestinal Endoscopy, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5642359/ Complex Refractory Oesophageal Stricture and Balloon Dilation — NCBI/PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10305297/

Balloon Dilation for Strictures: What to Expect? Read More »
What Is TIPS Procedure for Liver Disease?

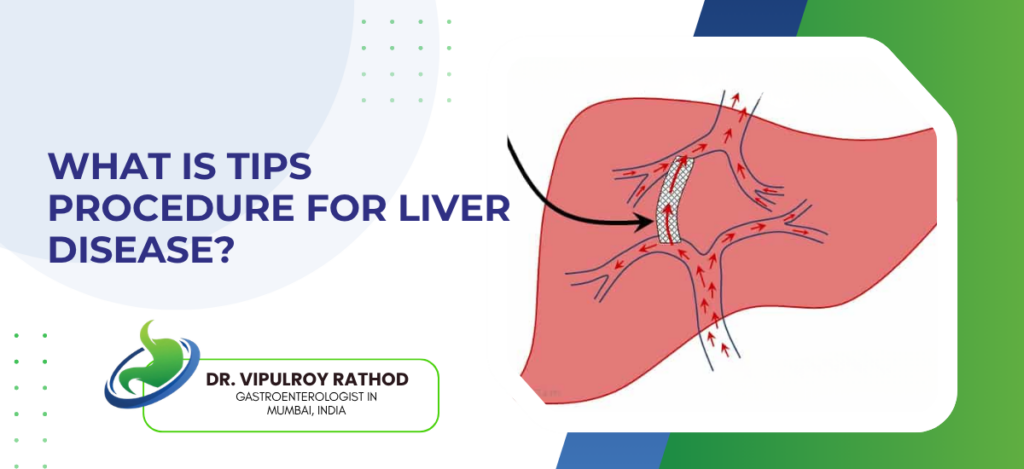
TIPS, transjugular intrahepatic portosystemic shunt, creates a channel inside the liver between the portal and hepatic veins to lower the pressure that builds up in portal hypertension. It’s performed through the jugular vein under imaging guidance, with no open surgery and a recovery considerably shorter than a surgical shunt. The procedure is used when cirrhosis complications, most often variceal bleeding or refractory ascites, stop responding to medical treatment and need a more direct pressure-reduction approach. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “TIPS isn’t a first-line treatment, but for patients where medical options have run out, it buys meaningful time. The key is selecting the right patient carefully, because TIPS can genuinely worsen liver function in someone whose hepatic reserve is already compromised, and that selection decision matters more than the procedure itself.” What Conditions Are TIPS Used For? TIPS targets the complications of portal hypertension that won’t settle with drugs or endoscopic management. Variceal bleeding that keeps recurring despite band ligation and pharmacotherapy is the clearest indication, where TIPS reduces the portal pressure driving the varices rather than repeatedly treating the varices themselves. Refractory ascites that require repeated paracentesis every few weeks is another strong indication, and TIPS relieves the pressure causing fluid accumulation and reduces the paracentesis burden substantially in suitable patients. Hepatic hydrothorax, fluid accumulating in the chest from portal hypertension, responds to TIPS in selected cases where thoracentesis has become the only management option. Hepatorenal syndrome can sometimes be reversed through TIPS when the pressure reduction restores enough renal perfusion, though this is reserved for carefully selected patients with sufficient residual liver function. Understanding how portal hypertension and liver decompensation interact is where a liver cirrhosis specialist decides whether TIPS is the right intervention or whether another route makes more clinical sense. What Are the Risks and Who Should Not Have TIPS? Patient selection is what separates a good TIPS outcome from a poor one, and the risks are real enough to make that selection non-negotiable. Hepatic encephalopathy is the most common complication, because TIPS diverts blood away from the liver and allows ammonia and other toxins to reach the brain rather than being cleared, which is why existing encephalopathy is a relative contraindication. Shunt stenosis or occlusion can develop over months and needs surveillance imaging to catch early, with covered stents now substantially reducing this problem compared to older bare metal designs. Patients with severe liver dysfunction are poor candidates because TIPS further reduces what little hepatic blood flow remains and can tip them into decompensation they can’t recover from. Heart failure and pulmonary hypertension push a significant volume of blood suddenly into the systemic circulation after TIPS, and an adequate cardiac workup before the procedure is essential in patients with any cardiac history. Managing the complications that lead patients to TIPS in the first place often involves a combination of endoscopic and medical treatment that endoscopy handles directly. Read more on pancreatic necrosis treatment to see how minimally invasive endoscopic approaches tackle other complex GI and hepatic complications without surgery. Why Choose Dr. Vipulroy Rathod for Liver Disease? Dr. Vipulroy Rathod has been managing cirrhosis complications and portal hypertension at Fortis Hospital Mulund for over 30 years, with endoscopic variceal management and EUS-guided assessment forming a core part of his practice. Patients approaching TIPS candidacy benefit from that depth of experience in identifying which complications can still be managed endoscopically and which genuinely need a shunt. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for liver cirrhosis and portal hypertension management. Book Appointment Call now Frequently Asked Questions What is the TIPS procedure? TIPS, or transjugular intrahepatic portosystemic shunt, is a procedure that creates a channel inside the liver between the portal and hepatic veins to reduce portal hypertension and its complications. What is TIPS used to treat? TIPS is used to treat portal hypertension complications including refractory variceal bleeding, recurrent ascites, hepatic hydrothorax, and in selected cases hepatorenal syndrome. Is TIPS a surgical procedure? No. TIPS is a minimally invasive interventional procedure performed through the jugular vein under imaging guidance, without open surgery and with significantly lower risk than a surgical shunt. What are the risks of the TIPS procedure? The main risks include hepatic encephalopathy, shunt stenosis or occlusion, and worsening liver function in patients with already compromised hepatic reserve, which is why careful patient selection is essential. Reference The Transjugular Intrahepatic Portosystemic Shunt in the Treatment of Portal Hypertension: Current Status — NCBI/PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3408669/ Effects of TIPS Treatment in Patients with Liver Cirrhosis and Portal Hypertension — NCBI/PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8270572/

What Is TIPS Procedure for Liver Disease? Read More »

Can Endoscopy Detect Gallbladder Cancer Early?

Gallbladder cancer is hard to catch early because it gives no reliable symptoms until it’s advanced, and standard ultrasound often misses the subtle wall changes that mark an early tumour. Endoscopic ultrasound narrows that gap by placing the probe directly against the gallbladder from inside the gut. For high-risk patients, that closer view is frequently what separates an early, treatable diagnosis from a late one. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “The problem with gallbladder cancer is that by the time it causes symptoms, it’s usually advanced. EUS lets us look far more closely at a suspicious gallbladder wall than an ultrasound can, and in the right patient that closer look is exactly what picks up disease at a stage where we can still do something about it.” How Does Endoscopy Detect Gallbladder Cancer? Proximity is what gives endoscopy its edge here, reaching detail external imaging routinely misses. Sitting the EUS probe against the gallbladder from inside the stomach or duodenum gives a high-resolution view of the wall, and early thickening or a small mass that ordinary ultrasound overlooks becomes visible. Tumour depth is where EUS genuinely outperforms other imaging. It shows how far a cancer has grown through the gallbladder wall, and that single measurement often decides whether early treatment is still possible. Regional lymph nodes come into view in the same session, letting the endoscopist judge local spread without waiting on separate scans that only add delay. Once a lesion looks suspicious, EUS-guided fine needle aspiration samples it on the spot and confirms or rules out cancer when imaging alone can’t give a clear answer. Judging whether a gallbladder finding deserves this closer look is where a gallbladder cancer specialist turns scattered imaging into a single clear assessment. Who Benefits Most from Endoscopic Assessment? Not every gallbladder complaint needs EUS, and matching it to the right patient is what makes it worthwhile. If someone has large gallstones, their baseline cancer risk is already higher, and a suspicious wall change on their ultrasound is worth examining with EUS rather than repeating the same scan. Polyps above 1 cm need proper characterisation. EUS reads their features far better than a follow-up ultrasound that only tracks whether they’ve grown. An unclear incidental finding on CT or ultrasound is exactly where EUS earns its place, separating harmless thickening from something that needs sampling and staging. Women over 50 from northern India sit in the highest-risk group globally, and a lower threshold for detailed endoscopic assessment makes sense whenever their imaging looks off. Seeing how EUS extends into other specialised diagnostic and treatment roles helps put its value here in context. Read more on EUS-guided drainage to see how EUS handles complex diagnostic and treatment tasks that routine imaging cannot. Why Choose Dr. Vipulroy Rathod for Gallbladder Cancer? Dr. Vipulroy Rathod has performed over 20,000 EUS procedures across more than 30 years at Fortis Hospital Mulund, in a region where gallbladder cancer runs far above global averages. That depth of EUS experience is what lets a suspicious gallbladder wall be assessed accurately and staged in a single workup rather than through scattered scans. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for gallbladder cancer detection and endoscopic staging. Book Appointment Call now Frequently Asked Questions Can endoscopy detect gallbladder cancer early? Endoscopic ultrasound can detect early gallbladder cancer by assessing wall thickening and tumour depth with greater accuracy than surface imaging, and allows tissue sampling when a lesion looks suspicious. What is the role of EUS in gallbladder cancer? EUS assesses how deeply a gallbladder tumour has grown and whether nearby lymph nodes are involved, providing local staging detail that ultrasound and CT cannot match, along with fine needle aspiration for diagnosis. Is ultrasound or EUS better for gallbladder cancer? Ultrasound is the first-line screening test, but EUS is more accurate for assessing tumour depth and local spread, making it valuable when a suspicious lesion needs closer evaluation. Why is gallbladder cancer hard to detect early? Gallbladder cancer rarely causes specific early symptoms, so it is often found incidentally after gallbladder removal or on imaging done for another reason, which makes targeted endoscopic assessment valuable in high-risk patients. Reference Gallbladder Cancer Treatment (PDQ) — National Cancer Institute, https://www.cancer.gov/types/gallbladder/hp/gallbladder-treatment-pdq Role of Endoscopic Ultrasound in the Diagnosis of Gallbladder Lesions — NCBI/PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC6134300/

Can Endoscopy Detect Gallbladder Cancer Early? Read More »

Colorectal Cancer Screening After 40 in India

Colorectal cancer is appearing earlier than it used to, and in India it’s too often caught at an advanced stage that screening could have prevented. Average-risk adults are advised to start at 45, yet a meaningful share of patients carry risk factors that bring that age down to 40 or below. Working out which group you belong to matters far more than treating 45 as a fixed rule for everyone. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Colorectal cancer in India is being diagnosed at younger ages and more advanced stages than it should be. The age cutoff is a starting point, not a finish line, because plenty of patients in their 30s and 40s walk in with findings everyone assumed were nothing. Screening timing should follow personal risk, not just a calendar.” Who Should Start Screening at 40 or Earlier? Personal risk, not age alone, decides when screening should begin, and several factors move it forward. If a parent or sibling has had colorectal cancer, your screening starts 10 years before their diagnosis age or by 40, whichever lands first. Long-standing IBD changes the picture entirely. Once Crohn’s or ulcerative colitis has been active in the colon for 8 years or more, surveillance colonoscopy every 1 to 3 years becomes part of routine management. Inherited syndromes such as Lynch or FAP move screening into the teens or twenties with much tighter intervals, placing these patients on a completely separate track. Symptoms override age. Rectal bleeding, a persistent shift in bowel habits, or unexplained weight loss warrants investigation immediately, whether or not someone has reached 40. Pinning down exactly where you sit on this spectrum is where a colorectal cancer specialist sets the right screening age and interval for you. Why Does Screening After 40 Matter So Much in India? Catching this cancer early transforms the outlook, and the Indian context makes that timing especially important. Cases in younger adults keep climbing. Colorectal cancer is turning up under 50 more often in India, which quietly undermines the old assumption that it belongs to older age groups alone. Most patients present late after months of blaming symptoms on piles or acidity, so screening catches disease before treatment becomes far harder and far more invasive. Colonoscopy prevents cancer rather than just finding it, because polyps get removed during the same session, stopping many tumours from ever forming. Nobody schedules it for you here. Without an organised screening programme, the initiative rests with the individual, which makes knowing your own risk and acting on it the deciding factor. Knowing precisely when to book that first scope comes down to your individual risk profile. Read more on first colonoscopy age to work out the right age for your first colonoscopy based on your personal risk factors. Why Choose Dr. Vipulroy Rathod for Colorectal Screening? Dr. Vipulroy Rathod has spent over 30 years performing advanced endoscopy at Fortis Hospital Mulund, with more than 80,000 procedures including thousands of colonoscopies. That volume translates into a careful reading of subtle findings, the kind that matters when a small polyp or unusual patch shows up during an otherwise routine screening scope. Physicians from 35 countries have trained under his approach at Fortis.  Book your consultation today with one of India’s most experienced specialists for colorectal cancer screening and colonoscopy. Book Appointment Call now Frequently Asked Questions At what age should Indians start colorectal cancer screening? Average-risk adults should begin colorectal cancer screening at 45, but those with a family history, IBD, or genetic syndromes often need to start at 40 or earlier depending on individual risk. Why is colorectal cancer screening important after 40 in India? Colorectal cancer is rising in younger Indian adults and is often diagnosed late. Screening after 40, especially for higher-risk individuals, catches disease early when it is far more treatable. What is the best colorectal cancer screening test? Colonoscopy is the most thorough screening test as it examines the entire colon and allows removal of polyps in the same session, unlike stool tests or sigmoidoscopy which are more limited. Who should start screening before 45? People with a first-degree relative who had colorectal cancer, those with inflammatory bowel disease for over 8 years, and anyone with genetic syndromes like Lynch or FAP should start screening earlier. References Colorectal Cancer Screening (PDQ) — National Cancer Institute, https://www.cancer.gov/types/colorectal/patient/colorectal-screening-pdq Colorectal Cancer Screening Guideline Update — American Cancer Society, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5943635/

Colorectal Cancer Screening After 40 in India Read More »

What Is APC for GI Bleeding?

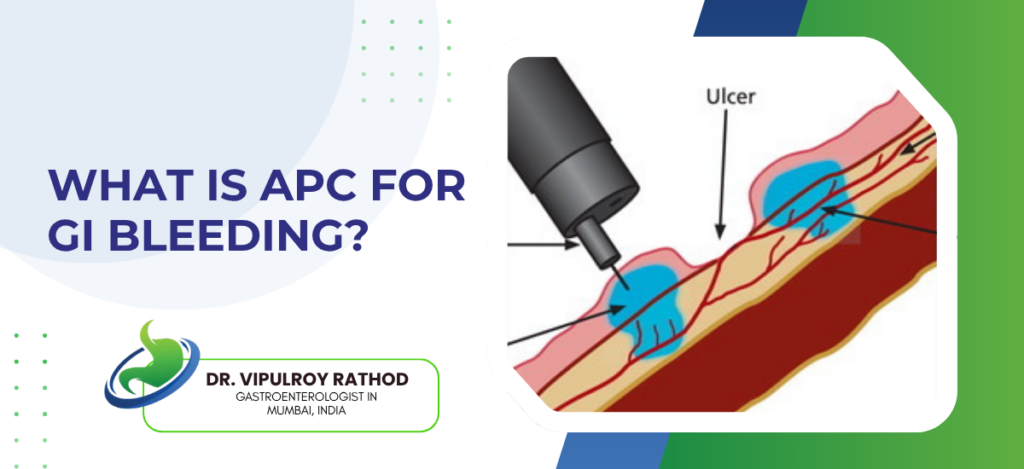
Argon plasma coagulation is a non-contact endoscopic technique that stops bleeding in the gastrointestinal tract without the probe ever touching the tissue. It works by delivering ionised argon gas, energised into plasma, that coagulates bleeding vessels and abnormal mucosa at a controlled depth through the endoscope. What makes it valuable is its ability to treat wide areas of diffuse bleeding evenly, the kind of bleeding where clipping a single vessel or injecting a spot simply isn’t practical, which is exactly where many patients would otherwise face repeat transfusions or surgery. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “APC has changed how we handle diffuse GI bleeding. When someone has bleeding spread across a wide area of mucosa, you can’t clip your way out of it. APC lets us treat that whole surface precisely, in the same session as the diagnosis, and most patients avoid both surgery and repeated transfusions as a result.” How Does APC Work and What Does It Treat? The technique combines precision with reach, treating sources that other methods struggle with. Passing a probe through the endoscope, APC releases argon gas that’s energised by high-frequency current into plasma, coagulating the target tissue at a controlled depth without any contact. Angiodysplasia and GAVE, the vascular lesions that cause slow chronic bleeding and anemia, respond particularly well because APC treats their scattered surface pattern evenly. In radiation proctitis, where the rectal lining bleeds diffusely after pelvic radiotherapy, APC ablates the fragile mucosa across a broad area that no single clip could address. For bleeding or obstructing tumours, APC offers palliative control, sealing the bleeding surface and easing symptoms in patients who aren’t surgical candidates. Deciding whether APC fits a given bleed needs endoscopic assessment of its source and pattern, which is where an APC bleeding control specialist matches the technique to the lesion. When Is APC the Right Choice for GI Bleeding? APC suits specific bleeding patterns, and knowing where it fits is what separates a controlled bleed from a surgical referral. Diffuse mucosal bleeding across a wide surface is APC’s clearest indication, since it treats the whole area evenly where clipping or injection would only address isolated points. When bleeding comes from vascular lesions, particularly angiodysplasia and GAVE, APC delivers reliable control that reduces the transfusion dependence these conditions often cause. In non-variceal upper GI bleeds such as certain ulcers, APC can supplement injection therapy to improve the durability of hemostasis at high-risk sites. Where surgery carries high risk, APC offers a same-day endoscopic alternative that controls the bleed without an incision or general anaesthetic in most cases. Understanding how APC fits within the wider range of endoscopic bleeding techniques helps put it in context. Read more on GI bleeding treatment to see how APC sits alongside clipping, injection, and band ligation in controlling GI bleeding without surgery. Why Choose Dr. Vipulroy Rathod for GI Bleeding? Dr. Vipulroy Rathod has been controlling acute and chronic GI bleeding at Fortis Hospital Mulund for over 30 years, using APC alongside clipping, injection, and variceal band ligation across a case volume few centres match. Patients arriving in active bleeding referred for a surgical opinion most often leave having had the source controlled endoscopically the same day, without ever meeting a surgeon. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for GI bleeding assessment and endoscopic bleeding control. Book Appointment Call now Frequently Asked Questions What is APC for GI bleeding? APC, or argon plasma coagulation, is a non-contact endoscopic technique that uses ionised argon gas to deliver controlled thermal energy, sealing bleeding vessels and abnormal tissue in the GI tract without touching them. What conditions is APC used to treat? APC treats angiodysplasia, gastric antral vascular ectasia, radiation proctitis, bleeding tumours, and diffuse mucosal bleeding across wide areas where clipping or injection is impractical. Is APC safe for GI bleeding? Yes. APC is minimally invasive, controls bleeding precisely without contact, avoids surgery in most cases, and allows same-day recovery, making it a safe alternative to repeat transfusion or operation. How does APC stop bleeding? APC releases ionised argon gas energised by high-frequency current, forming plasma that coagulates tissue at a controlled depth, sealing bleeding vessels evenly across the affected surface. References Improvement of Short-Term Outcomes for High-Risk Bleeding Peptic Ulcers With Addition of Argon Plasma Coagulation — NCBI/PMC, https://pubmed.ncbi.nlm.nih.gov/26266385/ Comparison of Argon Plasma Coagulation in Management of Upper GI Angiodysplasia and GAVE Hemorrhage — NCBI/PMC, https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3439282/

What Is APC for GI Bleeding? Read More »

Informational banner asking how silent gallstones are detected without symptoms; a hand holds a clear bag labeled 'GALLSTONES' with a red abdominal pain highlight on the right side.

How Are Silent Gallstones Detected Without Symptoms?

Gallstones don’t always cause pain or digestive trouble. Many people carry gallstones for years without ever knowing it, a condition doctors call silent gallstones or asymptomatic cholelithiasis. These stones form in the gallbladder but stay quiet, often turning up only when a scan is done for an entirely different reason. Dr. Vipulroy Rathod, a leading gastroenterologist in Mumbai, India, explains, “Most silent gallstones are found by accident during an ultrasound or scan ordered for something unrelated.  Once identified, the next step is understanding whether they need monitoring or treatment.” He adds that not every gallstone requires immediate intervention, but every case deserves a proper evaluation. With extensive experience in diagnosing and managing gallbladder and digestive conditions, Dr. Vipulroy Rathod helps patients understand what an incidental gallstone finding means for their health and what, if anything, needs to be done about it. Why do gallstones stay silent in the first place? Let’s look at what’s really happening inside the gallbladder. What Are Silent Gallstones and Why Do They Go Unnoticed? Silent gallstones are stones that form in the gallbladder without producing pain, digestive upset, or any other noticeable symptom. They are usually discovered incidentally, most often during an abdominal ultrasound, CT scan, or MRI performed for an unrelated health concern. Gallstones become “symptomatic” only when they block the flow of bile, irritate the gallbladder wall, or trigger inflammation. As long as a stone sits quietly without obstructing bile flow, it may never announce itself. What allows these stones to form without triggering any warning signs? Let’s look at the underlying factors. What Causes Gallstones to Form Without Symptoms? Gallstones develop when bile contains too much cholesterol or bilirubin, or when the gallbladder doesn’t empty completely. Several factors can contribute: Excess cholesterol in bile: When bile holds more cholesterol than it can dissolve, the excess can crystallize into stones. Poor gallbladder emptying: A gallbladder that doesn’t contract efficiently allows bile to sit and concentrate, encouraging stone formation. Excess bilirubin: Certain blood or liver conditions increase bilirubin levels, contributing to pigment stone formation. Obesity and rapid weight loss: Both can alter bile composition and increase gallstone risk. Family history: A genetic predisposition can make some individuals more prone to gallstones. Age and hormonal factors: Risk increases with age and can be influenced by hormonal changes, including pregnancy or hormone therapy. Had a scan mention gallstones you didn’t know about? Connect with a specialist to understand what it means for you. Book Appointment Call now Who is more likely to develop gallstones that stay hidden? Let’s look at the risk factors. Who Is at Risk of Developing Silent Gallstones? Since these stones don’t cause symptoms, how are they actually found? Let’s explore the detection methods. How Are Silent Gallstones Detected Without Symptoms? Because silent gallstones don’t announce themselves, they are almost always picked up through imaging or tests done for another purpose. Common ways they come to light include: Abdominal Ultrasound Ultrasound is the most common and reliable way gallstones are detected, often ordered to investigate vague abdominal complaints, during a routine health check-up, or for reasons unrelated to the gallbladder. Incidental Findings on CT or MRI Scans Gallstones are often a side effect (incidental find) that the physician finds when he/she does a scan (CT or MRI of the abdomen/spine, etc.) to detect problems in the organ near the gall bladder. Routine Health Check-Ups Comprehensive health screenings that include an abdominal ultrasound can reveal gallstones long before any symptoms would prompt a visit to the doctor. Blood Tests Liver enzymes are a group of enzymes made in the liver. These include the enzymes ALT, AST, and GGT. In some cases, elevated bilirubin levels or elevated enzymes can indicate gall-bladder related conditions or other liver diseases. Blood tests are not used to detect gall-stones but rather to point out other potential diseases that might lead the doctors to order imaging studies. Diagnosis Before Other Interventions If an individual plans for surgery or procedures, the doctor may first do an x-ray or an ultrasound to find out if there are any stones. On occasion, gallstones are found during x-ray or blood tests of the liver and gall-bladder done for other unrelated reasons. Once gallstones are identified, a gastroenterologist reviews the findings alongside the person’s overall health, symptoms (if any begin to appear), and risk factors to decide on the right next step. Once silent gallstones are found, does that automatically mean treatment is needed? Let’s look at how doctors decide. Should Silent Gallstones Always Be Treated? Not necessarily. Many people with silent gallstones never go on to develop symptoms and can simply be monitored over time. Doctors generally consider treatment when: The person has diabetes or a weakened immune system, which raises the risk of complications The gallbladder wall shows signs of calcification (“porcelain gallbladder”) Gallstones are unusually large There is a family history or personal risk factor for gallbladder cancer Symptoms such as pain, nausea, or digestive discomfort begin to appear For most people without these risk factors, a “watch and wait” approach with periodic review is a reasonable and commonly recommended path. What if silent gallstones are simply left alone without any follow-up? Let’s look at the possible risks. What Happens If Silent Gallstones Are Left Unmonitored? In most cases, silent gallstones remain harmless for years. However, without any follow-up, a small proportion of people may eventually develop: Biliary colic (sudden abdominal pain when a stone blocks bile flow) Gallbladder inflammation (cholecystitis) Blockage of the bile duct, leading to jaundice Inflammation of the pancreas (pancreatitis) Infection requiring urgent treatment This is why even asymptomatic gallstones are worth discussing with a specialist, so that a suitable monitoring plan can be put in place. Found gallstones during a routine scan? Reach out to a gastroenterologist for personalized evaluation and guidance. Book Appointment Call now Frequently Asked Questions 1. Can gallstones be present in one’s body without causing any symptoms? Really, quite a few individuals have gallstones present in their gallbladder even after an extended time

How Are Silent Gallstones Detected Without Symptoms? Read More »

Informational banner about stomach ulcers in teenagers, listing causes, symptoms, and treatment options; illustration of a person holding their stomach with a glowing red area.

Stomach Ulcer in Teenagers: Causes, Symptoms, and Treatment Options

Stomach Ulcer in Teenagers: Causes, Symptoms, and Treatment Options A stomach ulcer, also known as a gastric ulcer, is an open sore that develops on the inner lining of the stomach when its protective barrier becomes damaged. While commonly associated with adults, stomach ulcers in teenagers can also occur due to Helicobacter pylori (H. pylori) infection, long-term use of certain pain-relieving medicines, and digestive health factors. Symptoms like persistent stomach pain, nausea, acidity, or changes in appetite should not be ignored. Dr. Vipulroy Rathod, a leading gastroenterologist in Mumbai, India, explains, “Teenagers often ignore digestive symptoms, thinking they are temporary. Persistent stomach pain, acidity, or discomfort should be evaluated early to identify the underlying cause.” He further adds that accurate diagnosis helps provide targeted treatment and prevents complications. With extensive experience in endoscopy and management of digestive disorders, Dr. Vipulroy Rathod provides personalized stomach ulcer treatment for teenagers by identifying the underlying cause and choosing the most suitable approach. His expertise helps young patients receive safe, effective, and comprehensive care for stomach-related concerns. Why can teenagers develop stomach ulcers? Let’s explore the common factors that may affect stomach health during adolescence. What Are the Most Common Causes of Stomach Ulcers in Teenagers? Stomach ulcers in teenagers may develop due to several reasons, including infections, medications, and digestive habits. Common causes include: H.pylori infection: This bacterium can damage the stomach lining and cause long-term inflammation, leading to ulcer formation. Regular use of NSAIDs: Pain-relieving medicines such as ibuprofen or aspirin may irritate the stomach lining when used frequently or without medical guidance. Excess stomach acid production: Increased acid exposure can weaken the protective stomach lining. Poor dietary habits: Skipping meals, consuming excessive spicy or processed foods, and irregular eating patterns may worsen stomach irritation. Stress and lifestyle factors: While stress alone does not directly cause ulcers, it can increase symptoms and affect digestive health. Family history of digestive conditions: Some teenagers may have a higher risk due to genetic factors. Worried about recurring stomach problems? Connect with a specialist to understand the cause and suitable treatment options. Book Appointment Call now Could a common infection be affecting your teenager’s stomach health? Let’s discover the role of H. pylori in stomach ulcers. How Common Is H. pylori Infection Among Children and Teenagers? Helicobacter pylori infection is one of the most common causes of stomach ulcers worldwide. Many people acquire the infection during childhood, and it may remain unnoticed until symptoms appear. In children and teenagers, H. pylori can cause chronic inflammation of the stomach lining, which may eventually contribute to ulcer development. Testing is recommended when symptoms such as persistent abdominal pain, nausea, or unexplained digestive discomfort continue. What signs suggest a teenager may have a stomach ulcer? Let’s explore the symptoms that should not be overlooked. What Are the Symptoms of a Stomach Ulcer in Teenagers? Common gastric ulcer symptoms include: Burning or aching pain in the upper abdomen Stomach discomfort between meals or at night Nausea or vomiting Loss of appetite Feeling full quickly after eating Bloating and indigestion Unexplained weight loss Dark stools due to bleeding in severe cases Vomiting blood in rare complications Symptoms may vary from mild discomfort to more serious digestive problems. Are stomach ulcers, gastritis, and acid reflux the same condition? Let’s compare these common digestive problems. Stomach Ulcer vs Gastritis vs Acid Reflux: What Is the Difference? Although these conditions may cause similar symptoms like stomach discomfort, acidity, or nausea, they affect different parts of the digestive system. Understanding the difference helps in choosing the right diagnosis and treatment approach. Condition What Happens Common Symptoms Stomach Ulcer Open sores develop on the stomach lining due to damage or inflammation Burning stomach pain, nausea, vomiting, possible bleeding Gastritis Inflammation of the stomach lining without necessarily causing an open sore Upper abdominal discomfort, nausea, bloating Acid Reflux Stomach acid flows back into the food pipe Heartburn, sour taste, chest burning How do specialists confirm a stomach ulcer? Let’s explore the diagnostic process. How Do Doctors Diagnose Stomach Ulcers in Teenagers? Diagnosis of stomach ulcers in teenagers involves understanding symptoms, medical history, and identifying the underlying cause. Doctors may recommend the following evaluations: Medical History and Symptom Assessment Doctors review symptoms such as abdominal pain, acidity, nausea, appetite changes, and digestive problems. They also evaluate diet habits, family history, and previous stomach issues. Medication Review The use of pain-relieving medicines like NSAIDs is assessed, as frequent use may irritate the stomach lining and contribute to ulcer formation. H. pylori Testing Tests such as a breath test, stool test, or biopsy-based testing help detect Helicobacter pylori infection, a common cause of stomach ulcers. Blood Tests Blood tests may help identify anemia or signs of complications caused by long-term bleeding. Stool Tests Stool examination can detect hidden blood loss from an ulcer. Upper Gastrointestinal Endoscopy When required, an endoscopy allows a specialist to directly examine the stomach lining, identify ulcers, and take tissue samples for further evaluation. Accurate diagnosis helps determine the right stomach ulcer treatment and prevents possible complications. How are stomach ulcers treated in young patients? Let’s explore the approaches that help heal the ulcer and prevent recurrence. Treatment Options for Stomach Ulcers in Teenagers Treatment for stomach ulcers in teenagers depends on the underlying cause, severity of symptoms, and presence of complications. The main goal is to reduce acid irritation, heal the stomach lining, and address factors responsible for ulcer formation. Common treatment options include: Acid-Reducing Medicines Proton pump inhibitors (PPIs) and other acid-reducing medicines help decrease stomach acid production, allowing the ulcer to heal and reducing irritation. H. pylori Eradication Treatment If Helicobacter pylori infection is detected, a combination of antibiotics and acid-suppressing medicines is prescribed to eliminate the infection and prevent ulcer recurrence. Stopping or Changing NSAID Use If pain-relieving medicines such as NSAIDs are contributing to the ulcer, doctors may recommend stopping or changing them under medical supervision. Diet and Lifestyle Changes Maintaining regular meal timings, avoiding foods that trigger discomfort, and

Stomach Ulcer in Teenagers: Causes, Symptoms, and Treatment Options Read More »

Banner reading 'Top 7 Signs of Appendix Cancer' with a blue illustrated intestine on the right side and geometric shapes on a pale background.

Top 7 Signs of Appendix Cancer You Should Not Ignore

Appendix cancer is a rare type of gastrointestinal cancer that develops in the appendix, a small pouch connected to the large intestine. Since the appendix is located deep inside the abdomen and early symptoms are often mild or similar to common digestive issues, the condition may go unnoticed in many cases.  Understanding the signs of appendix cancer can help patients seek timely medical evaluation. Dr. Vipulroy Rathod, a  ace gastroenterologist in Mumbai, India, states,  “Unusual or persistent abdominal symptoms should not be ignored, especially when they continue despite routine treatment. Early assessment helps identify the cause and allows appropriate management.” He further emphasizes that advanced diagnostic methods play an important role in detecting complex gastrointestinal conditions. Dr. Rathod has more than 30 years of extensive experience in diagnosing and managing complex GI problems. He is known for his expertise in minimally invasive, endoscopic procedures. He focuses on accurate evaluation and personalized treatment strategies for gastrointestinal disorders and cancer-related digestive conditions. What happens when cancer develops in the appendix? Let’s understand this rare gastrointestinal condition. What Is Appendix Cancer? Appendix cancer occurs when abnormal cells grow uncontrollably in the appendix tissue. Although uncommon, it can affect different types of cells within the appendix and may behave differently depending on its type. Common types of appendix cancer include: Neuroendocrine tumors: These develop from hormone-producing cells and are among the more common appendix tumors. Appendiceal adenocarcinoma: These develop from glandular cells and may spread to surrounding tissues. Mucinous neoplasms: These produce mucus and can sometimes cause mucus accumulation inside the abdomen. Because symptoms are often unclear in the early stages, understanding the warning signs is important for timely diagnosis. Can appendix cancer be difficult to detect early? Let’s explore the reasons behind delayed diagnosis. Why Is Appendix Cancer Often Diagnosed Late? Appendix cancer is often diagnosed late because: The appendix is located deep within the abdomen. Early symptoms may be mild or absent. Symptoms can resemble common digestive problems. It is sometimes discovered accidentally during surgery for appendicitis. Routine screening tests are not commonly available for this cancer. Since symptoms can overlap with other gastrointestinal conditions, persistent changes should be evaluated by an experienced specialist. Could your symptoms indicate something more serious? Let’s explore the common symptoms of appendix cancer that should not be overlooked. Top 7 Signs of Appendix Cancer Persistent or Recurring Abdominal Pain Ongoing pain or discomfort in the abdomen, especially in the lower right side, may be one of the warning signs. Persistent pain that does not improve should be medically evaluated. Abdominal Bloating or Increasing Belly Size Unusual abdominal swelling or increasing belly size may occur due to fluid buildup or mucus accumulation inside the abdomen. Changes in Bowel Habits Changes such as constipation, diarrhoea, or altered stool patterns may occur when appendix-related growth affects nearby digestive structures. Unexplained Weight Loss or Loss of Appetite Unexpected weight loss or reduced appetite without a clear reason may indicate an underlying health issue requiring evaluation. Nausea, Vomiting, or Digestive Discomfort Persistent nausea, vomiting, or discomfort after meals may occur due to changes affecting the digestive system. Abdominal Mass or Feeling of Fullness Some patients may notice a lump, pressure, or a feeling of fullness in the abdomen. Symptoms Similar to Appendicitis Appendix cancer may sometimes present with symptoms similar to appendicitis, including abdominal pain, fever, and tenderness. Are appendix cancer and appendicitis the same condition? Let’s compare their symptoms and differences. Are Appendix Cancer Symptoms Different From Appendicitis? Although both conditions affect the appendix and may cause abdominal discomfort, they develop differently. The following comparison highlights how appendix cancer symptoms differ from those of appendicitis. Feature Appendix Cancer Appendicitis Cause Abnormal growth of cancer cells in appendix tissue Inflammation caused by blockage or infection of the appendix Onset of Symptoms Symptoms may develop slowly over weeks or months Symptoms usually appear suddenly and worsen quickly Abdominal Pain May cause persistent or recurring discomfort Usually causes sharp pain that often starts near the belly button and moves to the lower right abdomen Bloating or Abdominal Swelling May occur due to fluid or mucus buildup Less commonly associated with long-term swelling Digestive Changes May cause changes in bowel habits, fullness, or appetite loss Usually causes nausea, vomiting, and reduced appetite Fever May occur in some cases Common, especially with infection Diagnosis Requires imaging, biopsy, and specialist evaluation Usually diagnosed through symptoms, blood tests, and imaging Treatment Depends on cancer type and stage, including surgery and other therapies Usually treated with appendix removal surgery Are unusual abdominal symptoms lasting longer than expected? Let’s explore the signs that need timely medical evaluation. When Should You See a Doctor for Possible Appendix Cancer? You should seek medical advice if you experience: Persistent abdominal pain Unexplained weight loss Continuous bloating Changes in bowel habits Loss of appetite A feeling of abdominal fullness Repeated appendicitis-like symptoms Early evaluation helps identify whether symptoms are related to appendix cancer or another digestive condition. Need clarity about the diagnosis process? Let’s explore the tests and techniques used to accurately identify appendix cancer. How Is Appendix Cancer Diagnosed? Diagnosis may involve: Medical history and physical examination: Understanding symptoms and health background. Imaging tests: CT scans or MRI may help identify abnormal growths. Colonoscopy: Helps examine the large intestine and nearby areas. Blood tests: Certain markers may support diagnosis. Biopsy: Tissue examination confirms cancer type. Surgical evaluation: Some cases are diagnosed during appendix surgery. A detailed evaluation by a qualified gastroenterologist can help ensure accurate diagnosis. What happens after diagnosis? Let’s explore the available treatment approaches. Treatment Options After Appendix Cancer Diagnosis Treatment for appendix cancer is planned according to factors such as the tumor type, size, whether cancer has spread, and the patient’s overall condition. Common treatment options include: Surgery Surgery is often the primary treatment for appendix cancer. Depending on the extent of disease, procedures may include removal of the appendix, nearby tissues, or part of the colon if cancer has spread. Cytoreductive Surgery (CRS) In selected patients where

Top 7 Signs of Appendix Cancer You Should Not Ignore Read More »

Endoscopic Dilation

Endoscopic Dilation vs Strictureplasty for Crohn’s

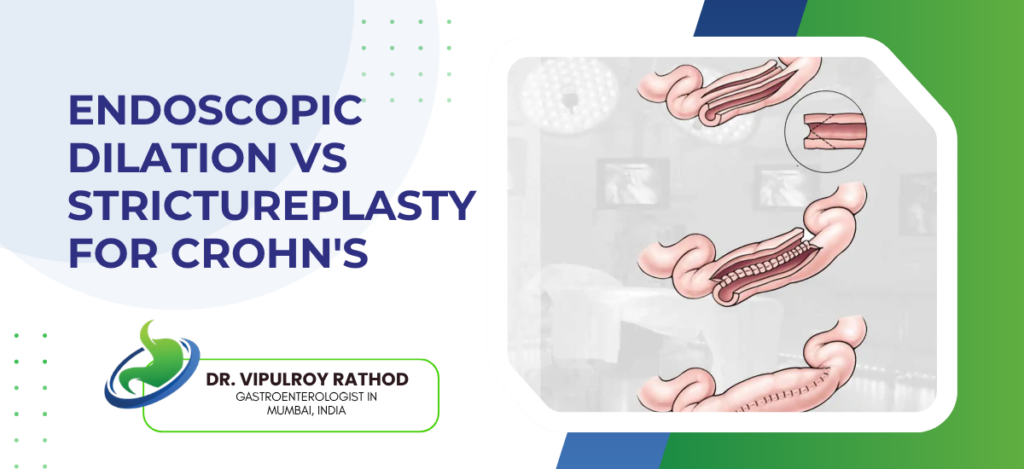
Crohn’s disease frequently narrows the bowel over time, and when a stricture starts causing obstruction, two main options exist to widen it without removing the segment. Endoscopic balloon dilation does this through the scope with no incision, while strictureplasty is a surgical procedure that reshapes the narrowed bowel to open it up. Both avoid resection and the bowel loss that comes with it, but they suit different strictures, and choosing correctly depends on the length, number, and location of the narrowing rather than a blanket preference for one approach. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “The goal in Crohn’s strictures is always to preserve bowel length, because these patients often face repeated narrowing over decades. Whether we dilate endoscopically or refer for strictureplasty comes down to the specific stricture, and matching the technique to it is what protects the patient from repeated resections down the line.” How Do the Two Approaches Differ? Each handles a stricture in a fundamentally different way. Factor Endoscopic Dilation Strictureplasty Approach Through the scope, no incision Surgical, bowel reshaped Best stricture Short, accessible Longer or multiple Recovery Same day Surgical recovery Durability May need repeat dilation More durable result Anaesthesia Sedation General anaesthesia Inflating a balloon across the stricture is how endoscopic dilation works, widening short fibrotic narrowings within reach of the scope and letting the patient go home the same day. Strictureplasty reshapes the narrowed segment surgically without removing it, opening up longer strictures or several close together that a balloon couldn’t address in one go. Because dilation is repeatable, it suits patients likely to develop further strictures, though restenosis means some will need the procedure more than once over time. Where the scope simply can’t reach a stricture or where multiple narrowings cluster along a segment, strictureplasty becomes the more practical and durable route. Deciding between them needs accurate assessment of the stricture, which is where a specialist in IBD management weighs length, access, and number before choosing the approach. Which Option Suits Which Patient? The right choice maps the technique to the specific stricture rather than the other way around. A single short stricture within reach is the clearest candidate for endoscopic dilation, sparing the patient surgery and an anaesthetic entirely. Multiple strictures along one segment are better served by strictureplasty, which can address several narrowings in a single planned operation rather than repeated scope sessions. For strictures the endoscope can’t access, particularly deeper in the small bowel, surgery often becomes necessary unless balloon-assisted enteroscopy can extend reach to them. When dilation has already failed repeatedly at the same site, moving to strictureplasty offers a more durable solution than continuing to re-dilate a stricture that keeps narrowing. Reaching strictures deep in the small bowel often depends on the type of scope used, and understanding how enteroscopy extends that reach is useful here. Read more on enteroscopy to see how it reaches small bowel strictures that a standard colonoscopy cannot. Why Choose Dr. Vipulroy Rathod for Crohn’s Strictures? Dr. Vipulroy Rathod has been managing Crohn’s strictures endoscopically at Fortis Hospital Mulund for over 30 years, with balloon-assisted enteroscopy since well before it became widely available in India. That reach lets him dilate small bowel strictures other centres would refer straight to surgery, preserving bowel length in patients facing decades of disease. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for Crohn’s stricture assessment and endoscopic dilation. Book Appointment Call now Frequently Asked Questions What is the difference between endoscopic dilation and strictureplasty for Crohn’s? Endoscopic balloon dilation widens a stricture through the scope without surgery, while strictureplasty is a surgical procedure that widens the narrowed segment by reshaping the bowel wall without removing it. Which is better for Crohn’s strictures, dilation or strictureplasty? It depends on the stricture. Short accessible strictures suit endoscopic dilation, while longer or multiple strictures, or those the scope cannot reach, are better managed with strictureplasty. Is endoscopic dilation for Crohn’s permanent? Not always. Endoscopic balloon dilation is effective but restenosis can occur, often requiring repeat dilation, whereas strictureplasty tends to give a more durable result for suitable strictures. Can strictures in Crohn’s be treated without surgery? Yes. Short fibrotic strictures within reach of the endoscope can be treated with balloon dilation, avoiding surgery, though longer or complex strictures may still require strictureplasty. Disclaimer: This blog is intended for informational and educational purposes only and should not be considered medical advice. Please consult a qualified gastroenterologist or healthcare professional for personalized diagnosis and treatment.

Endoscopic Dilation vs Strictureplasty for Crohn’s Read More »

Gallbladder Cancer Staging and Treatment in India

Gallbladder Cancer Staging and Treatment in India

Whether gallbladder cancer can be cured depends almost entirely on the stage at which it’s caught, which is why staging drives every treatment decision that follows. India carries one of the highest gallbladder cancer burdens in the world, particularly across the northern and eastern states, yet a large share of cases surface late or incidentally after gallstone surgery. Once the disease is identified, the TNM system maps how far it has spread, and that map determines whether surgery offers a cure or whether treatment shifts toward controlling the disease. According to Dr. Vipulroy Rathod, Gastroenterologist in Mumbai, “Staging is everything in gallbladder cancer. A tumour confined to the inner wall has a completely different outlook from one that’s reached the lymph nodes, and the treatment plan changes accordingly. Accurate staging upfront is what prevents both undertreating a curable cancer and overtreating one that’s already advanced.” How Is Gallbladder Cancer Staged? The TNM system grades three things: how deep the tumour has grown, whether nodes are involved, and whether it has spread. Stage What It Indicates Stage 0 Cancer confined to inner lining Stage I Invading muscle layer, no spread Stage II Through muscle into connective tissue Stage III Lymph nodes or nearby organs involved Stage IV Distant metastasis present Assessing tumour depth (T) establishes how far the cancer has grown through the gallbladder wall, which is the single biggest factor in whether curative surgery remains possible. Checking the regional nodes (N) determines whether the disease has reached nearby lymph nodes, a finding that moves a patient into a more advanced stage and reshapes the treatment plan entirely. Looking for distant spread (M) through CT or PET imaging confirms whether the cancer has reached the liver, lungs, or peritoneum, which separates operable disease from inoperable. Where imaging stays unclear, EUS adds precise local staging and allows tissue sampling, settling questions that surface scans alone can’t answer. Getting this assessment right is where a gallbladder cancer specialist combines imaging and endoscopic staging into a single accurate picture before any treatment begins. What Are the Treatment Options by Stage? Treatment follows the stage directly, ranging from curative surgery to disease control. For early-stage disease, surgical removal offers the best chance of cure, and cancers found incidentally after gallbladder removal sometimes need a second, extended resection to clear all involved tissue. Once the cancer reaches stage II or III, treatment usually combines extended surgery with chemotherapy, since clearing the tumour and affected nodes gives the strongest outcome at this point. In advanced or stage IV disease, the focus shifts to chemotherapy, targeted therapy, and symptom control rather than cure, with treatment aimed at extending and improving quality of life. When a tumour blocks the bile duct in inoperable cases, endoscopic biliary drainage relieves the jaundice and obstruction without surgery, which often makes systemic treatment possible. Accurate staging through the right imaging is what makes all of this possible, and knowing where endoscopy outperforms CT in staging is worth understanding. Read more on endoscopy vs CT to see how EUS improves staging accuracy for GI cancers where CT alone falls short. Why Choose Dr. Vipulroy Rathod for Gallbladder Cancer? Dr. Vipulroy Rathod has been staging and managing gallbladder cancer at Fortis Hospital Mulund for over 30 years, in a region where the disease is far more common than global averages. His EUS practice since 1998 means local staging and tissue diagnosis happen accurately in the same workup, so treatment decisions rest on a complete picture rather than a partial one. Physicians from 35 countries have trained under his approach at Fortis. Book your consultation today with one of India’s most experienced specialists for gallbladder cancer staging and treatment. Book Appointment Call now Frequently Asked Questions How is gallbladder cancer staged? Gallbladder cancer is staged using the TNM system, which assesses tumour depth into the gallbladder wall, lymph node involvement, and distant spread, guiding whether surgery or other treatment is appropriate. What are the treatment options for gallbladder cancer in India? Treatment depends on stage and includes surgical removal for early disease, chemotherapy and radiotherapy for advanced cases, and endoscopic biliary drainage to relieve obstruction in inoperable patients. Can early-stage gallbladder cancer be cured? Yes. Gallbladder cancer confined to the inner layers and found early, often incidentally after cholecystectomy, can be cured with surgery, sometimes requiring an extended resection. What is the role of EUS in gallbladder cancer staging? EUS provides accurate local staging by assessing tumour depth and regional lymph nodes, and allows fine needle aspiration for tissue diagnosis when imaging alone is inconclusive. Disclaimer: This blog is intended for informational and educational purposes only and should not be considered medical advice. Please consult a qualified gastroenterologist or healthcare professional for personalized diagnosis and treatment.

Gallbladder Cancer Staging and Treatment in India Read More »

Scroll to Top
Call Now Button